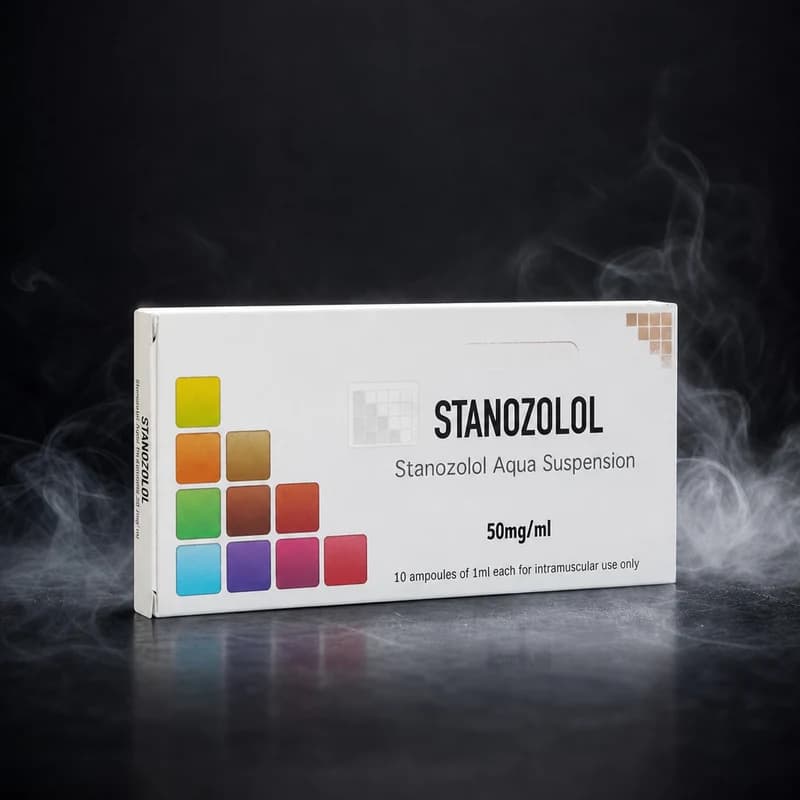
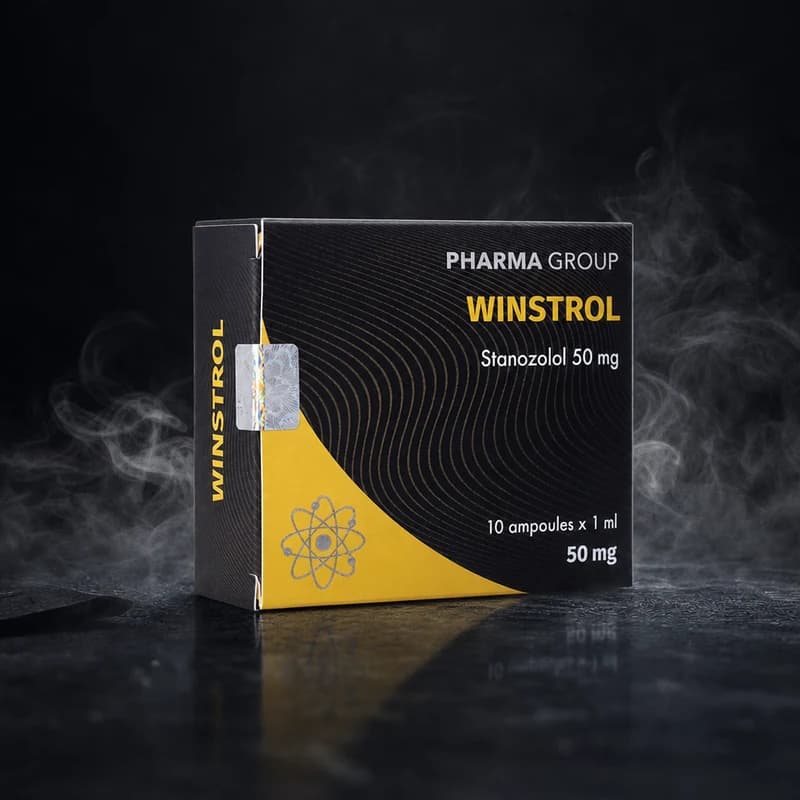
Stanozolol is a synthetic anabolic-androgenic steroid derived from dihydrotestosterone (DHT), characterised by a pyrazole ring fused to the steroid A-ring, which fundamentally alters its receptor binding profile and metabolic behaviour compared to its parent hormone.
Mechanism & Pharmacology of Stanozolol Injection
Stanozolol binds the androgen receptor with moderate affinity, exhibiting an anabolic-to-androgenic ratio of approximately 320:30 relative to testosterone — a ratio that reflects its structural resistance to 5-alpha reductase conversion, since the compound is already a DHT derivative and cannot be further reduced to a more androgenic metabolite. Unlike testosterone and nandrolone, stanozolol does not bind sex hormone-binding globulin (SHBG) in a competitive manner; rather, it actively displaces other androgens from SHBG, effectively increasing the proportion of free, bioavailable testosterone or any co-administered steroid in circulation. This SHBG displacement mechanism is one of the most pharmacologically significant synergistic properties in the compound's profile.
The injectable aqueous suspension form of stanozolol delivers the active compound as micronised particles suspended in water, rather than dissolved in oil as most injectable steroids are. This water-based delivery means there is no depot effect and absorption occurs relatively rapidly from the injection site. The elimination half-life of injectable stanozolol is generally cited in the range of approximately 24 hours, which is notably shorter than many oil-based injectables but longer than the oral tablet form. Anabolic activity is maintained through direct gene transcription modulation via androgen response elements in target tissues including skeletal muscle.
Critically, stanozolol does not aromatise. The aromatase enzyme cannot act on the altered A-ring structure created by the pyrazole modification, meaning oestrogen conversion is zero regardless of dose. There is consequently no oestrogen-mediated water retention, no gynaecomastia risk from this compound itself, and blood pressure implications differ from aromatising androgens. The compound does, however, exert a notable suppressive effect on endogenous testosterone production through hypothalamic-pituitary-gonadal (HPG) axis feedback, making post-cycle recovery planning a relevant consideration.
Stanozolol retains some progestogenic receptor activity, though this is considered clinically weak. Its hepatotoxic profile in injectable form is meaningfully lower than oral stanozolol, as first-pass hepatic metabolism is bypassed entirely. This is a pharmacologically important distinction for those managing bloodwork across a cycle.
Application Context & User Groups
The bodybuilding and performance community has used injectable stanozolol most prominently during preparation phases — contest prep, physique refinement cycles, and periods where lean tissue preservation alongside body composition improvement is the objective. Because the compound produces no subcutaneous water accumulation (no aromatisation, minimal mineralocorticoid activity), the aesthetic result under low body fat conditions is characteristically a harder, more vascular, and more striated appearance. This makes stanozolol injection a staple reference compound in cutting-focused protocols.
Stanozolol injection is used across a relatively broad demographic within performance sport. Physique athletes — including competitive bodybuilders, fitness models, and classic physique competitors — represent one primary group, drawn by the dry, non-bloating muscular quality the compound produces. Strength athletes in weight-class sports historically valued stanozolol for strength-to-weight ratio improvements without significant mass gain. Amateur gym users approaching their first or second anabolic cycle often encounter stanozolol as a commonly recommended lower-androgenic option, though its interaction with lipid panels (particularly LDL elevation and HDL suppression) is a real physiological consideration that distinguishes it from milder compounds.
Stanozolol stacks extensively with non-aromatising androgens such as trenbolone, masteron (drostanolone), and primobolan during cutting protocols. It is also used alongside testosterone base compounds, where its SHBG displacement effect enhances the free fraction of co-administered testosterone. In lean bulking contexts, some athletes use stanozolol injection at lower frequencies to add density without mass accumulation.
The aqueous injection route requires attention to injection site tolerance. Water-based suspensions are known to cause more local discomfort than oil-based preparations, and injection frequency varies from every day to every other day depending on concentration and individual protocol. Athletes experienced with oil-based injectables often note a perceptible difference in site comfort and should plan accordingly.
Range & Selection by Concentration and Pack Size
The category spans three concentration tiers — 50 mg/ml, 100 mg/ml, and 150 mg/ml — with pack formats including 10 ml vials, 10×1 ml ampoules, and 3×1 ml ampoules. This breadth accommodates users ranging from those managing conservative introductory protocols to experienced competitors using higher daily doses across extended preparation periods.
50 mg/ml is the foundational and most widely available tier, represented by well-established products from multiple pharmaceutical-grade manufacturers. Stanobolin-50 by BM Pharmaceuticals and Strombaject by Balkan Pharmaceuticals are both presented at this concentration in 10×1 ml ampoule format, making them convenient for athletes who prefer single-use dosing and appreciate the quality assurance implied by pre-sealed ampoule packaging. Winstrol Depot by Desma, offered in 3×1 ml ampoules, represents the historically referenced pharmaceutical presentation of this compound and suits athletes sourcing a compact ampoule format. Winstrol Inj by Dragon Pharma in a 10 ml vial at 50 mg/ml provides a multi-draw option that suits those planning a longer cycle without mid-cycle resupply. At 50 mg/ml, users typically administer between 50 and 100 mg per day or every other day, making this tier versatile for both conservative and moderate protocols.
100 mg/ml offers a middle-ground concentration that reduces injection volume by half for a given dose. This is practically relevant since water-based injections in larger volumes contribute disproportionately to site discomfort. The 100 mg/ml tier suits more experienced users who have established injection tolerance and require higher daily totals without the volume increase.
150 mg/ml represents the highest concentration available in this category and is exemplified by StanoTrex 150 mg/ml by Concentrex Labs in a 10 ml vial format. This tier is intended for experienced athletes running higher-dose protocols during the final weeks of contest preparation, where dosing of 150 mg daily or near-daily may be employed. The 10 ml vial format at this concentration provides excellent economy of volume across a multi-week protocol. Injection discomfort at this concentration warrants careful site rotation and, for some athletes, warming the vial slightly before drawing to improve suspension consistency.
Winstrolad by Driada Medical at 50 mg/ml in 10×1 ml ampoules is a further option for athletes prioritising the convenience and sterility assurance of individual ampoule presentation at the foundational concentration tier.
Selection guidance: athletes new to injectable stanozolol are well-served beginning at the 50 mg/ml tier in ampoule format to assess individual site tolerance. Those with prior injectable experience and established protocols should evaluate the 100 or 150 mg/ml tiers to optimise injection volume and cycle logistics.
Frequently Asked Questions
What is the difference between injectable stanozolol and oral stanozolol tablets?
Injectable stanozolol bypasses first-pass hepatic metabolism entirely, which results in meaningfully lower hepatotoxic stress compared to the oral tablet form. The active compound and core pharmacology are identical — the same anabolic ratio, the same SHBG displacement effect, and the same absence of aromatisation — but the injectable route is generally considered the more liver-friendly administration method for equivalent doses.
Why is injectable stanozolol water-based rather than oil-based like most injectable steroids?
Stanozolol has very low solubility in oil at practical concentrations, so it is formulated as a micronised aqueous suspension rather than an oil solution. This affects both the absorption profile — producing a shorter effective half-life of roughly 24 hours — and the injection experience, as water-based suspensions are commonly associated with greater localised discomfort than oil-based injectables.
Which concentration tier is most appropriate for a first injectable stanozolol cycle?
The 50 mg/ml tier is the most appropriate starting point for those new to injectable stanozolol. It allows for precise, lower-volume dosing while the individual establishes tolerance to the water-based suspension. Products such as Strombaject by Balkan Pharmaceuticals or Stanobolin-50 by BM Pharmaceuticals in pre-sealed ampoule formats are particularly well-suited for this purpose.


 Pro Choice