Contraindications: Stanover is contraindicated in individuals with pre-existing hepatic impairment, active cardiovascular disease, or clinically significant dyslipidaemia. Women who are pregnant or planning pregnancy must not use this compound. Individuals with a personal or family history of prostate pathology should avoid androgenic-anabolic compounds without specialist medical supervision.
Side_Effects: HDL cholesterol suppression is the primary cardiovascular concern and is measurable within two weeks at bulking doses. Androgenic effects including acne, accelerated scalp hair loss, and increased sebum production are possible, particularly in genetically predisposed individuals. Joint dryness — sometimes noted with stanozolol — may be more pronounced during bulking phases when training loads are higher. Women face virilisation risk at any dose above 10mg EOD.
Monitoring: Obtain a full lipid panel (direct HDL, LDL, triglycerides), liver enzymes (ALT, AST), haematocrit, and blood pressure at baseline before starting Stanover. Repeat lipid and hepatic panels at the midpoint and end of each cycle. HDL values falling below 35mg/dL on direct enzymatic assay or ALT/AST rising above twice the laboratory reference range should prompt immediate dose reduction or cessation.
PCT: Stanozolol clears plasma within three to five days of the final injection due to its short aqueous-suspension half-life, allowing PCT to begin sooner than with long-ester base compounds. Standard PCT — typically a SERM such as tamoxifen or clomiphene for four weeks — should be timed relative to the clearance of the longest-acting compound in the bulking stack, not stanozolol itself. Endogenous testosterone recovery should be assessed by serum LH, FSH, and total testosterone at four weeks post-PCT.

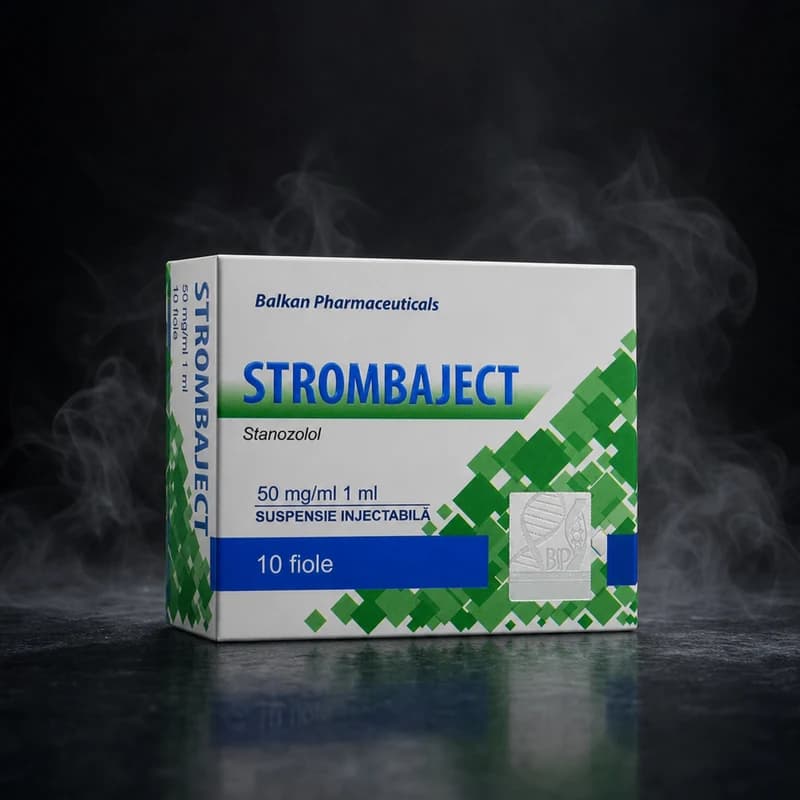 Established Brand






