Contraindications: Do not use if you have existing hepatic impairment, cardiovascular disease, prostate or breast carcinoma, or are pregnant or planning pregnancy. Stanozolol is not appropriate for individuals under 21 years of age. Microdosing does not eliminate compound-specific contraindications — lower dose frequency reduces peak exposure but does not neutralise absolute contraindications.
Side Effects: Even at microdose levels, injectable stanozolol can suppress HDL cholesterol and elevate LDL in a dose-duration-dependent pattern. Joint discomfort resulting from reduced synovial fluid is reported at all dose levels. Androgenic effects including acne, scalp hair acceleration, and voice deepening remain possible, particularly in women. Daily injection frequency increases cumulative site-injection burden — rotate sites diligently.
Monitoring: Obtain a lipid panel, hepatic enzyme screen (ALT, AST), and haematocrit baseline before starting. Repeat lipid and liver panels at four-week intervals during the cycle. Track injection sites for nodule formation or persistent redness — indicators of inadequate aseptic technique or particle accumulation. Women should self-assess for virilisation signs weekly.
PCT: Stanozolol suppresses the hypothalamic-pituitary-gonadal axis at all clinically relevant doses including microdose ranges. A structured PCT protocol — typically commencing within 48–72 hours of the final injection — using a SERM such as Nolvadex or Clomid is required to restore endogenous testosterone production. Duration and dosing of PCT should be guided by a qualified sports-medicine physician.

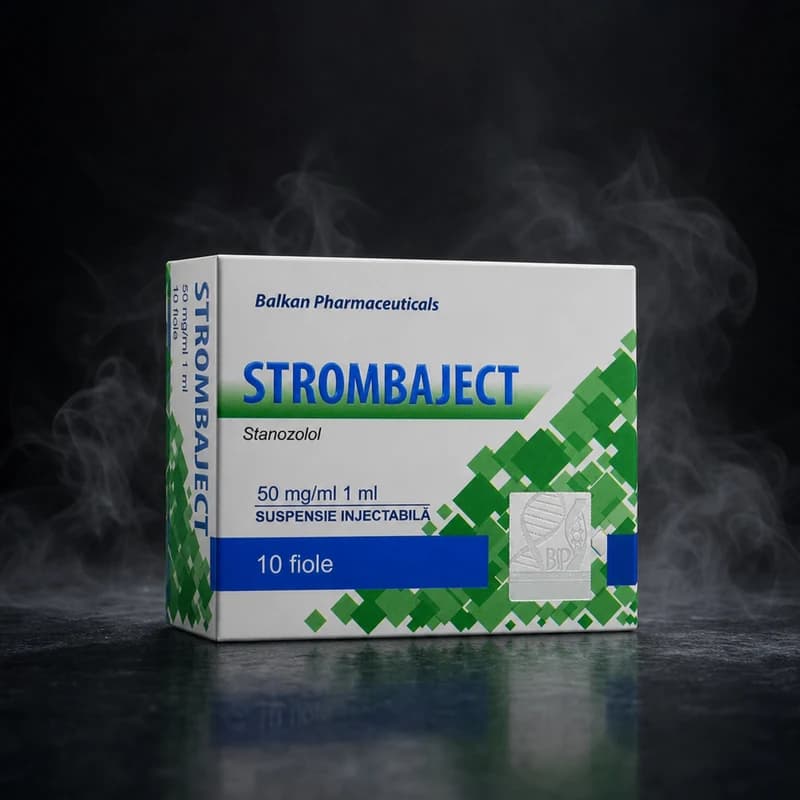 Established Brand






