Contraindications: Not for use by individuals with active hepatic impairment, diagnosed cardiovascular disease, prostate carcinoma, or breast carcinoma. Women who are pregnant or may become pregnant must not use this product. Individuals under 21 years of age should not use androgenic-anabolic compounds.
Side Effects: Stanozolol suppresses HDL cholesterol and elevates LDL; this cardiovascular lipid shift is dose- and duration-dependent. Hepatotoxic potential exists even via the injectable route at sustained higher doses such as those used during a frontload. Androgenic effects including accelerated male-pattern hair loss, acne, and virilisation in female users have been documented in clinical literature. SHBG suppression is pronounced and modifies the free-androgen fraction of any co-administered compound.
Monitoring: Obtain a full lipid panel and hepatic enzyme profile (ALT, AST) at baseline — before the frontload dose — and repeat at weeks 3 and 6. Blood pressure measurement should occur weekly during the loading phase given the acute androgenic input on day one. Haematocrit monitoring is advisable on cycles exceeding four weeks.
PCT: Endogenous testosterone suppression necessitates a structured post-cycle therapy protocol beginning approximately 48–72 hours after the final stanozolol injection, aligned with its short aqueous-suspension clearance window. Standard PCT agents (SERMs such as nolvadex or clomid) should run for four weeks minimum. A full hormonal blood panel confirming baseline LH, FSH, and total testosterone restoration is recommended before initiating any subsequent cycle.

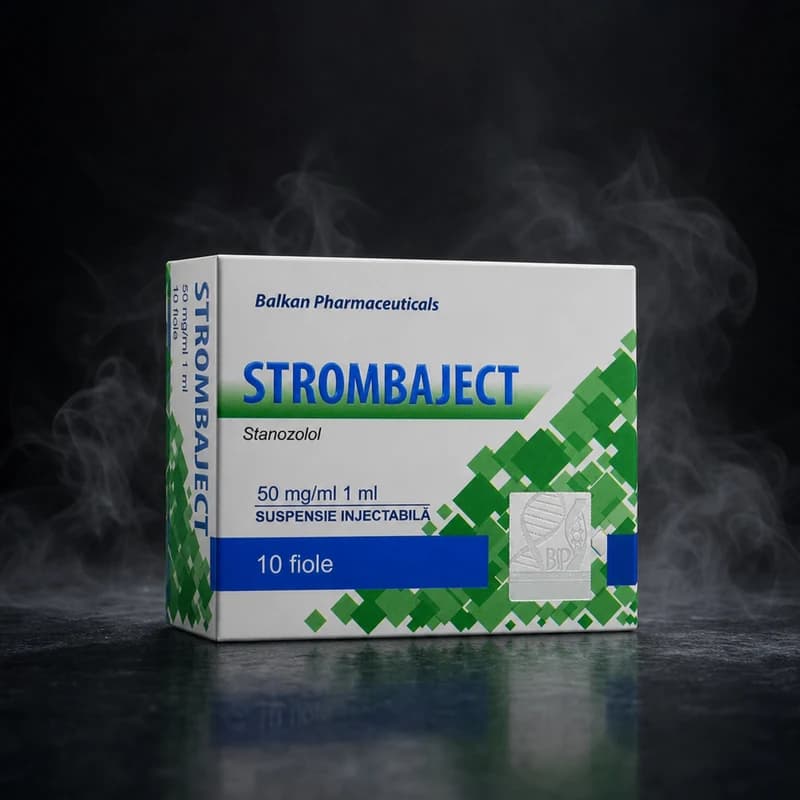 Established Brand






