contraindications: Contraindicated in individuals with prostate or breast carcinoma — androgen receptor activation in these tissues is contraindicated regardless of compound.
Not for use during pregnancy or breastfeeding; virilisation of the foetus presents an irreversible developmental risk.
Contraindicated in patients with severe hepatic impairment; stanozolol exerts direct hepatic androgen receptor effects independent of the route of administration.
Individuals with a history of hypersensitivity to stanozolol or any aqueous suspension excipient should not use this product.
side_effects: Androgenic effects: acne, accelerated androgenic alopecia in genetically predisposed individuals, virilisation in female users.
Hepatotoxicity: elevated liver enzymes (ALT/AST) documented with stanozolol across both oral and injectable routes; liver function monitoring is mandatory.
Dyslipidaemia: HDL suppression and LDL elevation have been quantified in clinical lipid panels within two weeks of stanozolol initiation.
Joint discomfort: stanozolol's SHBG-reducing action lowers circulating oestrogen to a degree that reduces synovial lubrication, increasing connective tissue injury risk.
Cardiovascular strain: left ventricular structural changes have been documented with prolonged androgenic compound use; blood pressure monitoring is advised.
monitoring: Liver function panel (ALT, AST, GGT) at baseline and at four-week intervals during active cycle.
Full lipid panel (HDL, LDL, triglycerides) at baseline and mid-cycle to quantify dyslipidaemic shift.
Blood pressure measured weekly; androgenic compounds can elevate systolic pressure through fluid and haematocrit effects.
Haematocrit at baseline — stanozolol's erythropoietic activity can raise haematocrit into thrombogenic range with extended use.
pct: Post-cycle therapy (PCT) with a SERM — typically tamoxifen or clomiphene — initiated 24–48 hours after the final injection to restore endogenous HPG axis activity.
Duration of PCT should correlate with cycle length; a six-to-eight-week cycle typically warrants a four-week PCT minimum.
Off-cycle blood work including total testosterone and LH/FSH at weeks two and four post-cycle confirms HPG axis recovery trajectory.

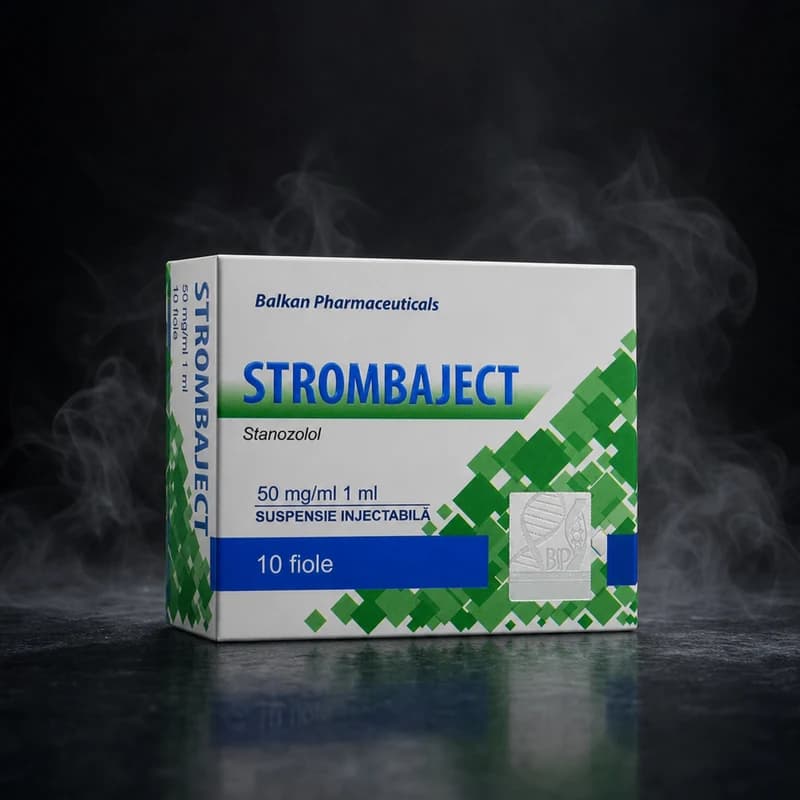 Established Brand






