Contraindications: Absolute contraindications include active hepatic disease, confirmed polycythaemia, and concurrent use of any 17-alpha-alkylated oral anabolic steroid. Concurrent use with anticoagulants (particularly warfarin) requires clinical supervision — stanozolol potentiates anticoagulant effect as documented in pharmacokinetic interaction data. Patients with pre-existing lipid disorders should not combine stanozolol with any additional androgen that suppresses HDL.
Side Effects: Hepatocellular stress (elevated ALT/AST), HDL suppression, LDL elevation, increased blood viscosity through erythrocytosis, androgenic effects (acne, hair loss in genetically susceptible individuals), and tendon collagen alteration with extended use. Severity scales non-linearly with co-administered compounds sharing the same adverse pathways.
Monitoring: Liver enzyme panel (ALT, AST, GGT) and direct HDL/LDL assay at baseline, week 2, and week 4 of any protocol involving a combination. Complete blood count to monitor haematocrit — values exceeding 52% in males signal erythrocytosis requiring protocol adjustment. Blood pressure twice weekly when stanozolol is paired with testosterone at any dose.
PCT: Post-cycle therapy should commence within 3–5 days of the final ampoule, as stanozolol's plasma clearance is substantially faster than esterified androgens. A SERM-based PCT (tamoxifen or clomiphene per standard protocol) is recommended; the rapidity of stanozolol clearance means HPG axis suppression resolves faster than with long-ester compounds, but any co-administered long-ester base compound dictates the actual PCT start window.

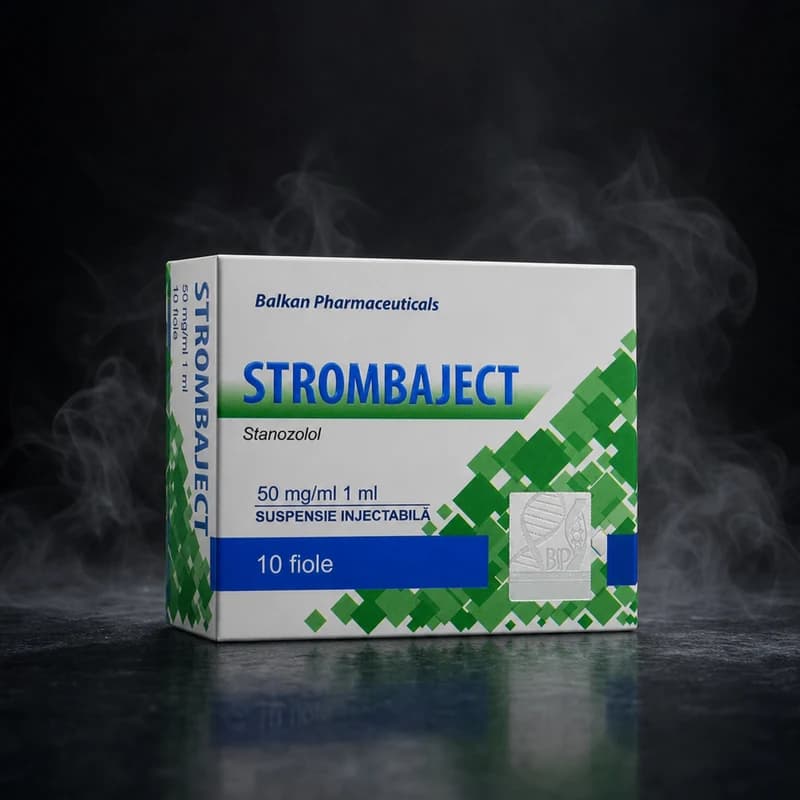 Established Brand






