Stanozolol Oral: Mechanism and Pharmacology
Stanozolol is a synthetic anabolic-androgenic steroid derived from dihydrotestosterone (DHT), modified at the A-ring with a pyrazole group fused at positions 2 and 3, which fundamentally alters its binding behaviour and metabolic fate. Because it originates from DHT, stanozolol cannot be converted to oestrogen via aromatase; this single structural fact makes it categorically different from testosterone-based orals, where oestrogenic side effects are a persistent management challenge.
Stanozolol binds the androgen receptor with moderate affinity — its relative binding affinity sits at approximately 20–30% that of testosterone — yet its anabolic-to-androgenic ratio is rated at roughly 320:30 compared with testosterone's baseline of 100:100. This disparity arises partly because stanozolol also interacts with progesterone receptors and sex hormone-binding globulin (SHBG). Stanozolol displaces bound testosterone from SHBG with notable efficiency, effectively raising the free testosterone fraction in circulating blood without adding exogenous testosterone itself. SHBG binds stanozolol with very low affinity, which means a higher proportion of the compound remains pharmacologically active in plasma.
The oral form is 17-alpha-alkylated at carbon 17, the structural modification that grants hepatic stability and allows meaningful systemic bioavailability after first-pass metabolism — estimated at approximately 30–60% depending on the individual. This alkylation is also responsible for the compound's well-documented hepatotoxic potential, which is dose- and duration-dependent. Oral stanozolol carries a plasma half-life of roughly 9 hours, requiring once- or twice-daily administration to maintain stable blood concentrations. Peak plasma levels are typically reached within 1–2 hours post-ingestion. The compound is excreted primarily via urine and remains detectable in standard sports drug testing for approximately 3 weeks following cessation of use.
Stanozolol does not convert to progesterone-active metabolites in a clinically meaningful way for most users, though it does exhibit partial progesterone receptor agonism. Unlike many anabolics, it does not cause significant water retention, a property directly linked to its lack of oestrogenic activity and its mild effect on aldosterone pathways.
Application Context and User Groups
Within competitive bodybuilding and physique sport, stanozolol oral has maintained a consistent presence over several decades precisely because its pharmacological profile aligns well with specific pre-competition objectives. Athletes seeking to reduce subcutaneous water retention, preserve lean muscle during a caloric deficit, and improve the visual density and definition of musculature have historically favoured stanozolol in the final 6–10 weeks before a competition.
Stanozolol enhances nitrogen retention in muscle tissue and increases red blood cell production, supporting both recovery rates and muscular endurance. The compound stimulates protein synthesis through androgen receptor activation in skeletal muscle, while its SHBG-suppressing action creates a more anabolic endocrine environment without the requirement for high androgen doses. This property makes it popular in combination strategies where stanozolol is "stacked" alongside longer-acting compounds — its contribution to free androgen availability amplifies the effect of other agents in the cycle without adding aromatisable androgens.
Track and field athletes and swimmers historically used stanozolol for strength gains that were not accompanied by bodyweight increases — a practical advantage in weight-class or power-to-weight-ratio sports. This aspect of the compound's profile, rather than its cosmetic effects, explains its long history in athletics.
For bodybuilders in a bulking phase, stanozolol oral is rarely the primary compound of choice. Its inability to aromatise means no oestrogen-mediated collagen synthesis benefit, and some users report increased joint discomfort during heavy loading — attributed to stanozolol's reduction of synovial fluid lubrication via oestrogen suppression. This is a clinically recognised effect that distinguishes stanozolol protocols from those built around wet androgens.
A brief note: content on this page is for informational purposes related to product selection; it does not constitute medical advice.
Range and Selection by Concentration and Pack Size
The stanozolol oral category here comprises 26 products from 24 manufacturers, available in three concentration tiers — 10mg, 20mg and 50mg per tablet — across pack sizes ranging from 20 to 105 tablets. Understanding the practical distinctions between these tiers assists in making an appropriate selection.
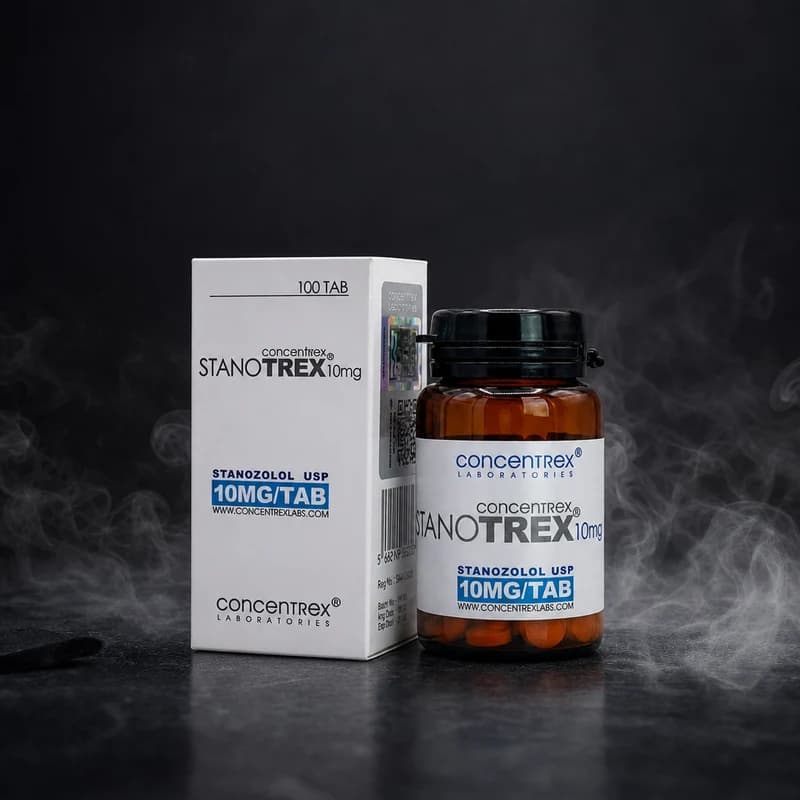
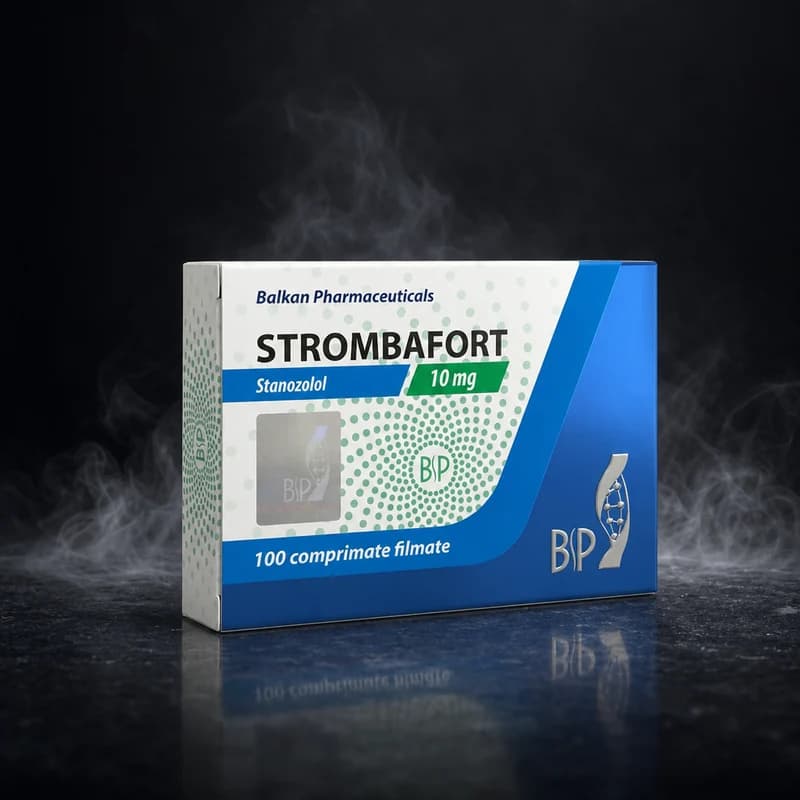
10mg per tablet products form the largest segment of this category and suit users who prefer fine-grained dose control or who are running lower total daily doses of 20–40mg. Strombafort by Balkan Pharmaceuticals (10mg/tab, 100 tablets) is a well-established reference product in this tier, manufactured by one of Eastern Europe's most consistently stocked pharmaceutical operations. StanoTrex Tablets by Concentrex Labs (10mg/tab, 100 tablets) offers an alternative at the same concentration and pack size for those who prefer a different manufacturer provenance. Winstrol 50 by Dragon-Pharma, despite the brand name, is formulated at 10mg per tablet in a 100-tablet pack, providing a larger unit count per pack — practical for longer-duration protocols. For users running a standard 30–40mg daily dose, a 100-tablet pack at 10mg provides roughly 25–33 days of supply.
20mg per tablet products occupy a middle tier that reduces daily tablet count without the dose jumps inherent to 50mg tablets. Pro-Winstrol by Beligas Pharmaceuticals (20mg/tab, 50 tablets) is the principal representative at this concentration. A 50-tablet pack at this strength delivers 1,000mg total — structurally equivalent to 100 tablets at 10mg — offering the same total supply with fewer tablets to manage. This tier is well-suited to users already familiar with stanozolol who have established an effective dose and want logistical simplicity.
50mg per tablet products are typically selected by more experienced users, or those following protocols where higher single-dose administration is deliberately intended. Winstrol 10 by Dragon-Pharma (50mg/tab, 100 tablets) stands out in this tier as a high-volume, high-potency pack delivering 5,000mg total stanozolol — suitable for longer cycles or shared protocols. Stanos by Driada Medical (10mg/tab, 100 tablets) rounds out the 10mg tier from a newer-to-market but increasingly available manufacturer. At 50mg per tablet, dose splitting is less practical unless tablets are divisible, making this tier more appropriate for straightforward once-daily or twice-daily protocols rather than the measured micro-adjustments possible with 10mg tablets.
Selecting by pack size also reflects cycle length planning: 20-tablet packs offer a short trial window, while 100- and 105-tablet packs support full 6–10 week protocols without reorder interruption.
Frequently Asked Questions
What is the difference between 10mg and 50mg stanozolol oral tablets in practical use?
The concentration difference affects dosing flexibility. At 10mg per tablet, users can precisely adjust their daily intake in small increments — useful for dose-finding or lower-range protocols between 20–40mg daily. At 50mg per tablet, each unit represents a full dose for many users, reducing tablet count but making fine adjustment impractical unless the tablet can be halved.
Does oral stanozolol cause water retention?
No. Stanozolol does not aromatise to oestrogen, which is the primary hormonal driver of water and sodium retention in anabolic steroid use. This makes it a distinctly "dry" compound. Users often select it specifically to avoid the soft, fuller appearance associated with oestrogen-active androgens, particularly during pre-competition preparation phases.
How does oral stanozolol compare to injectable stanozolol in terms of effect?
Both forms share the same active molecule. The oral form is 17-alpha-alkylated for hepatic stability, resulting in greater liver stress but convenient administration. Injectable stanozolol (suspension) has a shorter half-life and bypasses first-pass metabolism. Some users report the injectable form produces marginally harder muscular effects, though evidence is largely anecdotal; pharmacologically, the active compound is identical.


 Lab Tested