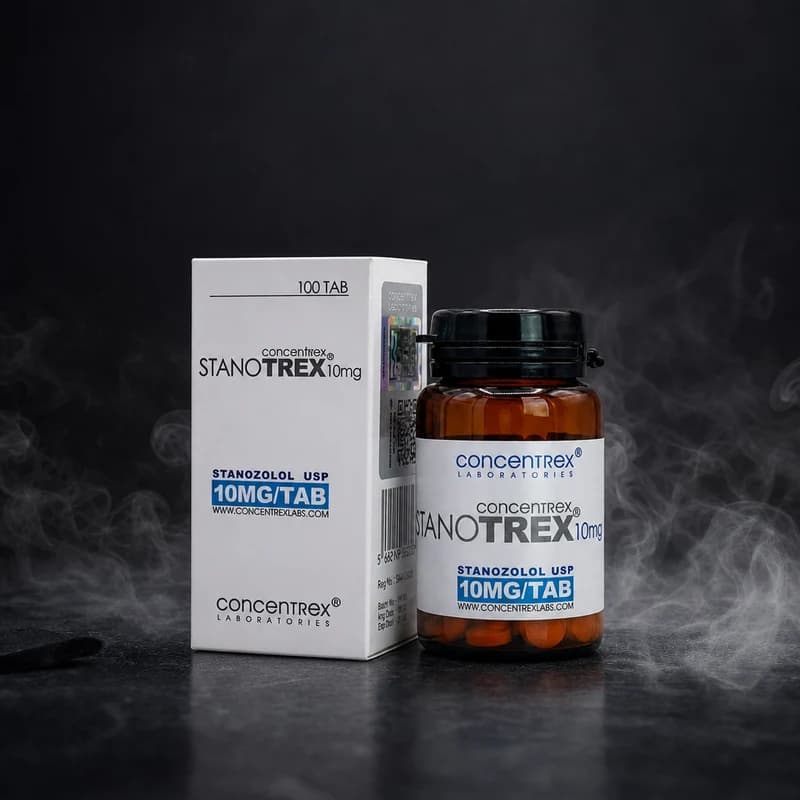
Contraindications: Not for use by individuals under 18 years of age, women who are pregnant or breastfeeding, or anyone with a confirmed diagnosis of hepatic impairment, prostatic carcinoma, or hypersensitivity to stanozolol. Pre-existing cardiovascular conditions — particularly dyslipidaemia — represent a relative contraindication requiring physician review before use.
Side Effects: Hepatic enzyme elevation (ALT, AST) is the primary dose-dependent risk associated with oral stanozolol via the 17α-alkylated metabolic pathway. Additional effects include LDL elevation, HDL suppression, acne, increased hair loss in genetically predisposed individuals, and clitoral or penile sensitivity changes. Virilisation risk in women is significant even at low doses.
Monitoring: Pre-cycle baseline bloodwork covering LH, FSH, total testosterone, ALT, AST, and lipid panel is mandatory. Repeat liver enzymes at cycle week 2. Full hormonal and lipid re-assessment at end of active cycle, and again at PCT weeks 2 and 4, provides the objective data framework for determining recovery completeness.
PCT: Post-cycle therapy is required after every stanozolol cycle. The short oral clearance window (approximately 36–45 hours) allows SERM initiation within 24–48 hours of the final dose. Tamoxifen at 20 mg/day for four weeks or clomiphene at 50 mg/day tapering to 25 mg/day over four weeks are the referenced SERM frameworks. Do not rely on subjective wellbeing as a PCT endpoint — use LH, FSH, and testosterone bloodwork to confirm axis recovery before ending the SERM protocol.

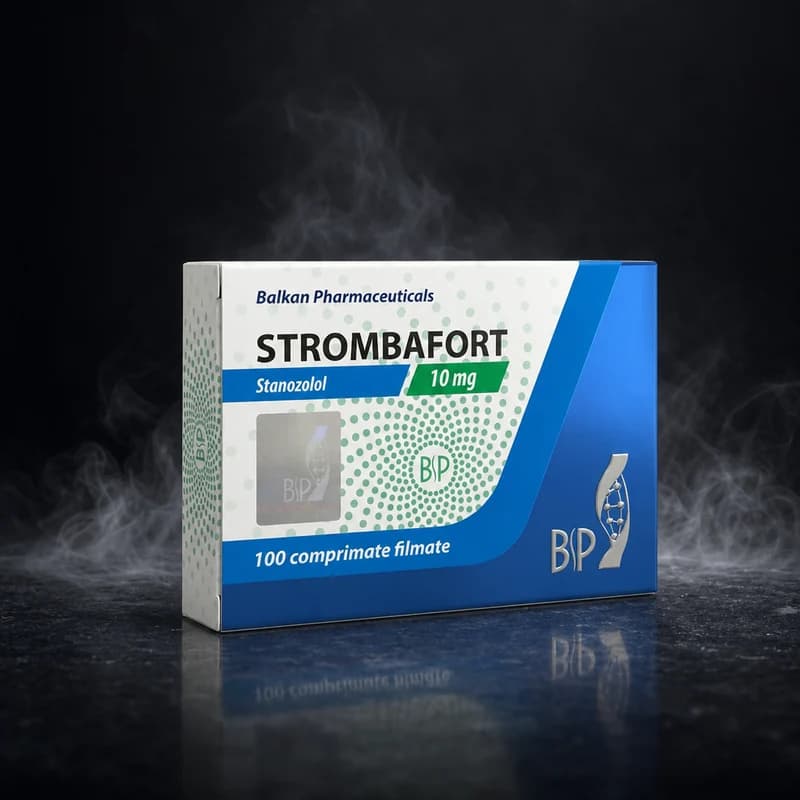 Lab Tested