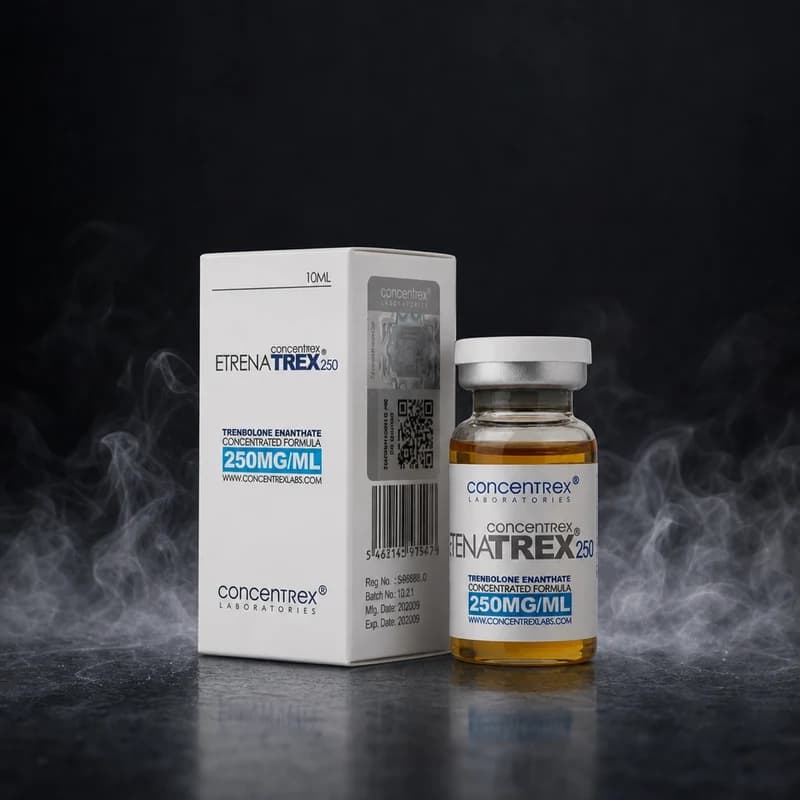
Contraindications: Trenbolin-200 is contraindicated in individuals with known hypersensitivity to Trenbolone Enanthate or any oil-based excipient in the formulation. It must not be used by women of childbearing potential due to strong virilisation risk. Individuals with existing hepatic impairment, active cardiovascular disease, prostate carcinoma, or breast cancer should not administer this compound. Adolescents and individuals under 21 with open growth plates are excluded from use.
Side Effects: Androgenic effects include acne, accelerated scalp hair loss (in genetically predisposed individuals), and pronounced virilisation in female users. Cardiovascular effects include suppression of HDL cholesterol, elevation of LDL, increased haematocrit, and potential left ventricular hypertrophy with prolonged high-dose use. Trenbolone-specific effects include night sweats, reduced aerobic capacity ('tren cough' post-injection in a minority of users), insomnia, and heightened aggression. Due to the 7–10 day half-life, adverse effects may persist for up to two weeks after the final dose.
Monitoring: Lipid panel (HDL/LDL), haematocrit, and blood pressure should be assessed at baseline and at 4–6 week intervals during active cycling. Liver enzyme monitoring (ALT, AST) is advisable despite Trenbolone's non-hepatotoxic classification, as stack combinations may confound results. Electrocardiographic monitoring is recommended for cycles exceeding 12 weeks at doses above 400mg/week. Kidney function markers (creatinine, eGFR) should be tracked in users with pre-existing renal concerns.
PCT: Because Trenbolone Enanthate carries a 7–10 day half-life, the last active compound clears plasma approximately 14 days post-final injection. PCT initiation should be delayed until this clearance window has elapsed — typically day 14–16 post-cycle. Standard PCT employs a SERM (Clomiphene or Tamoxifen) for 4–6 weeks to restore endogenous HPG axis function, which is substantially suppressed by Trenbolone's potent androgen receptor binding.

 High Concentration