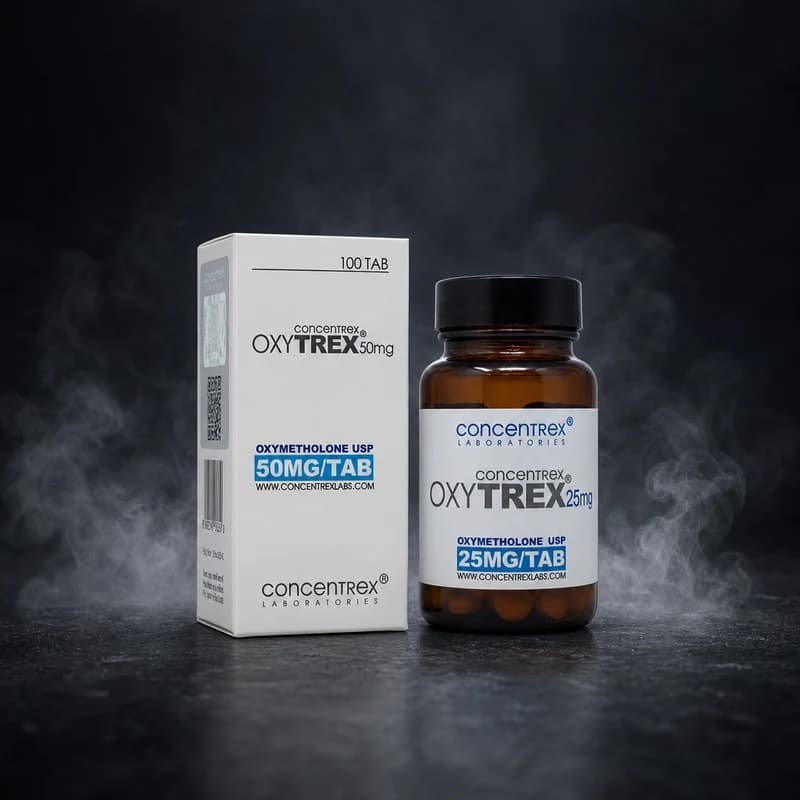
Contraindications: Pro-Anadrol is contraindicated in individuals with existing hepatic dysfunction, cholestatic liver disease, or elevated baseline liver enzymes (ALT/AST more than twice the upper limit of normal). Prostate carcinoma or breast carcinoma in male users represents an absolute contraindication. Females who are pregnant or may become pregnant must not use this compound. Individuals with a history of hypersensitivity to 17-alpha alkylated androgens should not initiate use.
Side Effects: Hepatotoxicity is the primary risk associated with oral 17-alpha alkylated compounds; Pro-Anadrol carries this risk proportional to dose and duration. Fluid retention and estrogenic-pattern effects (gynecomastia, oedema) can occur despite the compound's structural DHT lineage, likely via non-aromatase mechanisms. Blood pressure elevation, erythrocytosis (excess red blood cell production), and HDL suppression are documented in clinical trial data on therapeutic Oxymetholone use. Androgenic side effects including acne, accelerated scalp hair loss in predisposed individuals, and virilisation in females are dose-dependent.
Monitoring: Liver function panels (ALT, AST, ALP, bilirubin, GGT) should be assessed at baseline and at weeks 4 and 8 of any cycle. Complete blood count monitoring for erythrocytosis is recommended given Oxymetholone's documented haematopoietic activity. Lipid panels (HDL, LDL, total cholesterol, triglycerides) and blood pressure readings should be recorded at minimum every four weeks. Any elevation in liver enzymes exceeding three times the upper limit of normal warrants immediate cycle cessation.
PCT: Post-Cycle Therapy should commence within 72 hours of the final Pro-Anadrol tablet, taking into account that plasma clearance of oral Oxymetholone occurs over approximately 36–45 hours (based on half-life pharmacokinetic modelling). SERMs such as Tamoxifen (Nolvadex) or Clomiphene Citrate are the standard PCT agents for hypothalamic-pituitary-gonadal axis recovery. A minimum 4-week PCT protocol is recommended after cycles exceeding 6 weeks in duration. Liver support agents (TUDCA or UDCA at clinical dosing) should be continued for 4 weeks post-cycle to support hepatic recovery from 17-alpha alkylation-associated stress.

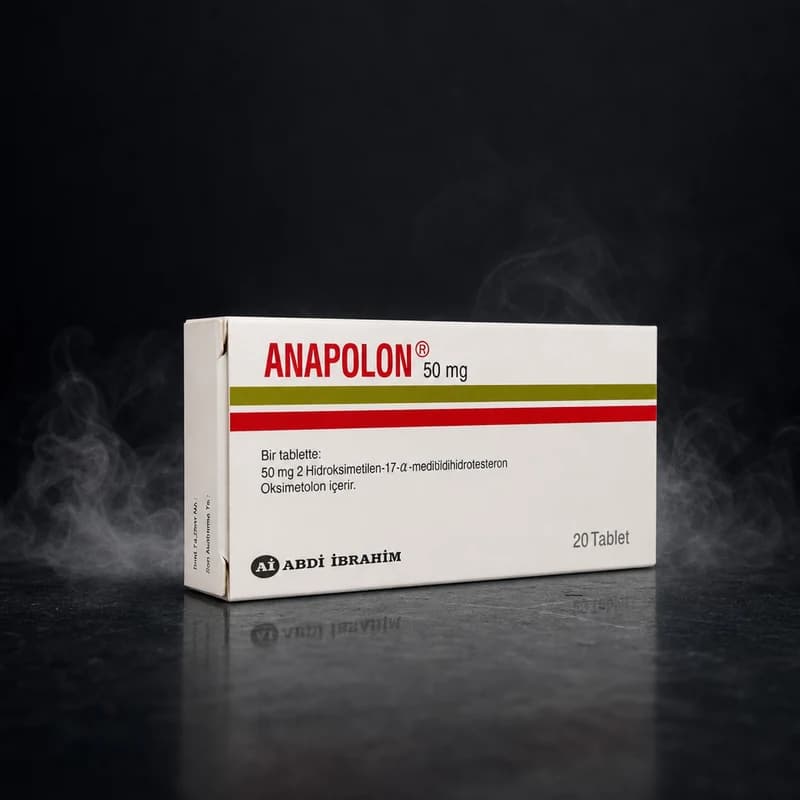 Lab Tested