Contraindications: OxyTrex is contraindicated in individuals with pre-existing hepatic impairment, diagnosed diabetes mellitus (type 1 or type 2), impaired fasting glucose or insulin resistance at baseline, prostate or breast carcinoma, active cardiovascular disease, or known hypersensitivity to 17-alpha-alkylated androgens. Women who are pregnant or may become pregnant must not use this compound under any circumstances.
Side Effects: Hepatotoxicity is the primary dose-limiting concern with any 17-alpha-alkylated oral; OxyTrex users should anticipate transient ALT and AST elevation. Metabolic side effects specific to this compound include reduced insulin sensitivity, impaired fasting glucose, and dyslipidaemia characterised by suppressed HDL and elevated LDL. Additional effects include fluid retention, elevated blood pressure, androgenic changes (acne, accelerated hair thinning in predisposed individuals), and suppression of endogenous testosterone production.
Monitoring: Mandatory monitoring includes: fasting glucose (weekly during cycle), ALT/AST (at baseline, week 3, and cycle end), complete lipid panel (at baseline and cycle end), blood pressure (at least biweekly), and haematocrit given Oxymetholone's known erythropoietic activity. Any fasting glucose reading exceeding 6.1 mmol/L (110 mg/dL) on two consecutive measurements warrants immediate dose reduction or cessation.
PCT: Endogenous testosterone suppression following OxyTrex use requires a structured post-cycle therapy protocol. A standard SERM-based approach (Tamoxifen 20 mg/day or Clomiphene 50 mg/day for 4–6 weeks) is the recommended framework, initiated after allowing sufficient clearance time. Insulin sensitivity and hepatic function should be reassessed at 4 weeks into PCT to confirm metabolic recovery is tracking appropriately.

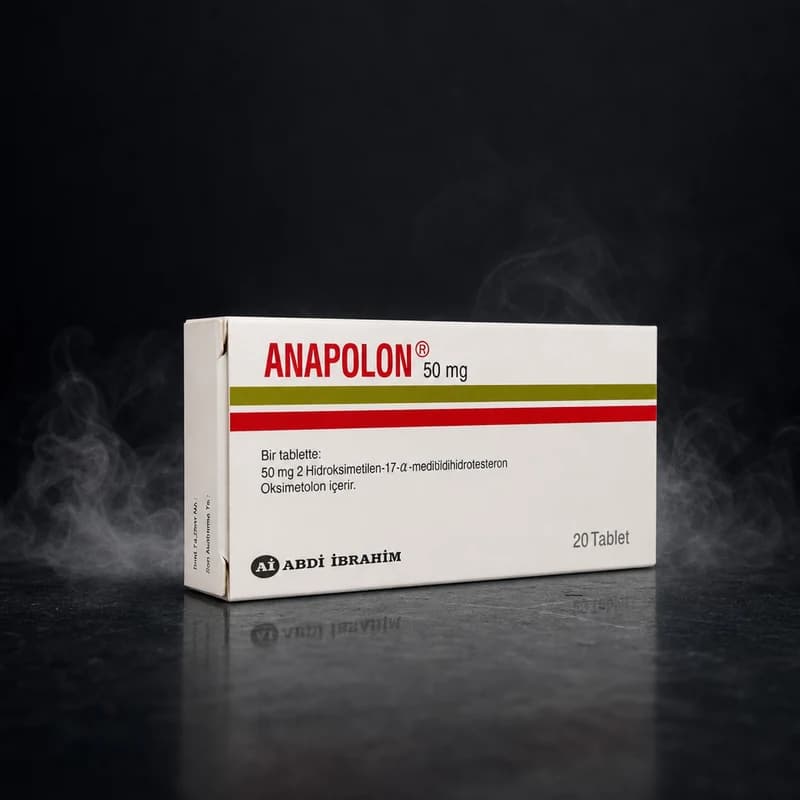 Lab Tested






