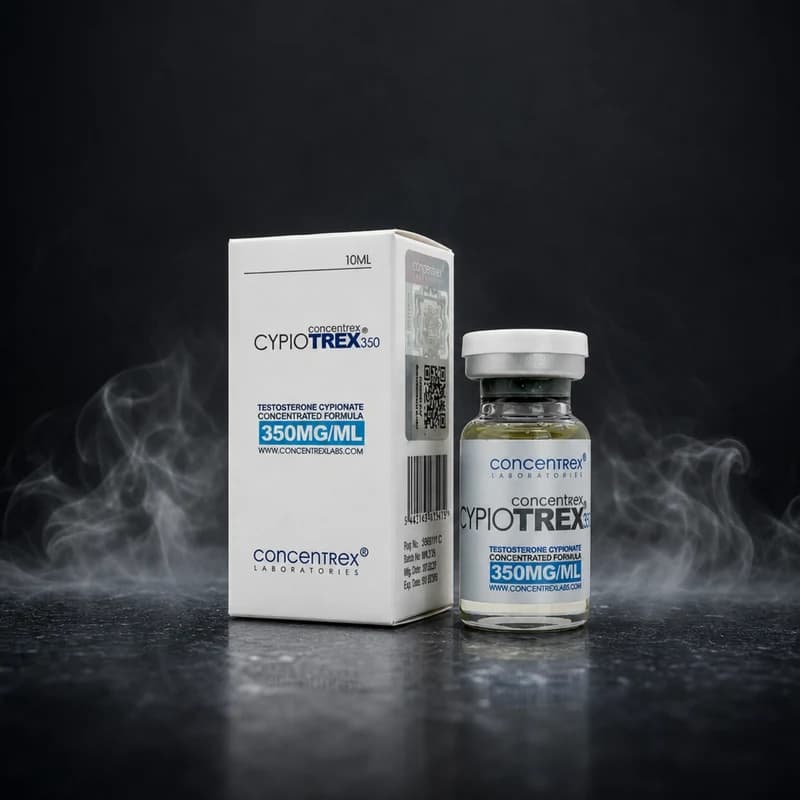
Contraindications: Not indicated for individuals with existing androgen-sensitive malignancies, hypercalcaemia, active liver pathology, or untreated severe cardiovascular disease. Contraindicated during pregnancy. Men with polycythaemia or uncontrolled hypertension should not use without specialist medical supervision.
Side Effects: Elevated haematocrit and erythrocytosis require routine full blood count monitoring. Aromatisation to oestradiol may produce fluid retention, gynaecomastia, and mood variability — aromatase inhibitor co-administration should be guided by serum oestradiol results, not empirical dosing. Androgenic effects including accelerated scalp hair loss and acne are genetically predisposed. Endogenous testosterone suppression is universal and proportional to dose and duration.
Monitoring: Obtain baseline bloods before cycle initiation: total testosterone, LH, FSH, haematocrit, lipid panel, and hepatic enzymes. Repeat at cycle midpoint and at cessation. Androgen receptor downregulation is not directly measurable in clinical practice, but plateau in strength and body composition gains despite maintained serum levels is a practical surrogate indicator.
PCT: Initiate SERM-based post-cycle therapy after allowing sufficient time for serum cypionate levels to decline following the final injection. Standard SERM options include tamoxifen or clomiphene under medical guidance. Off-cycle duration should be at least equal to cycle duration to permit both HPG axis recovery and androgen receptor density normalisation.

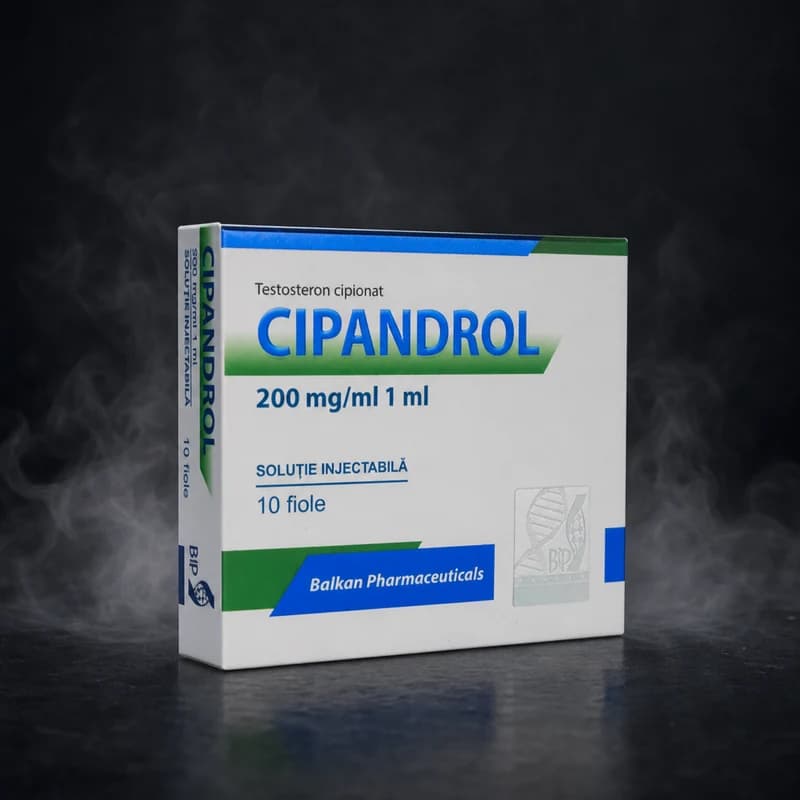 Established Brand