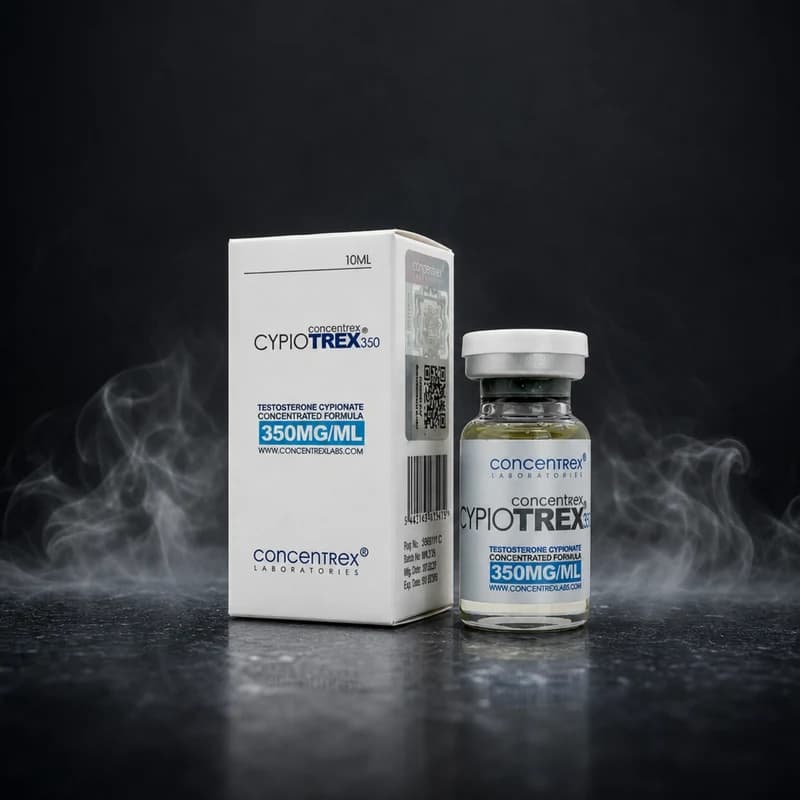
Contraindications: Testosterone Cypionate is contraindicated in individuals with androgen-dependent carcinoma of the prostate or breast, active polycythaemia, untreated severe obstructive sleep apnoea, or hypersensitivity to any component of the formulation including the carrier oil. Combining with HGH is additionally contraindicated in active malignancy, as growth hormone may accelerate tumour proliferation.
Side Effects: Supraphysiological androgen exposure may produce erythrocytosis (elevated haematocrit), oestrogen-related fluid retention, gynaecomastia, acne, androgenic alopecia in genetically predisposed individuals, and HPG-axis suppression. HGH co-administration introduces additional considerations: carpal tunnel syndrome, joint fluid retention, transient glucose dysregulation, and dose-dependent acromegalic features with prolonged high-dose use.
Monitoring: Full blood panels are required at baseline, Week 8, and cycle end: haematocrit, serum testosterone, oestradiol, LH/FSH, lipid profile, fasting glucose, HbA1c, liver enzymes, and PSA in males over 40. Serum IGF-1 should be measured by radioimmunoassay at Week 6 of HGH use to confirm therapeutic elevation without excessive supraphysiological overshoot.
PCT: Allow the cypionate ester to clear — approximately 14 days post-final injection — before initiating post-cycle therapy. Standard SERM-based PCT (clomiphene or tamoxifen) is required to restore endogenous HPG-axis function following suppression. HGH does not suppress the HPG axis and does not require PCT; discontinue it gradually rather than abruptly to avoid rebound IGF-1 suppression.

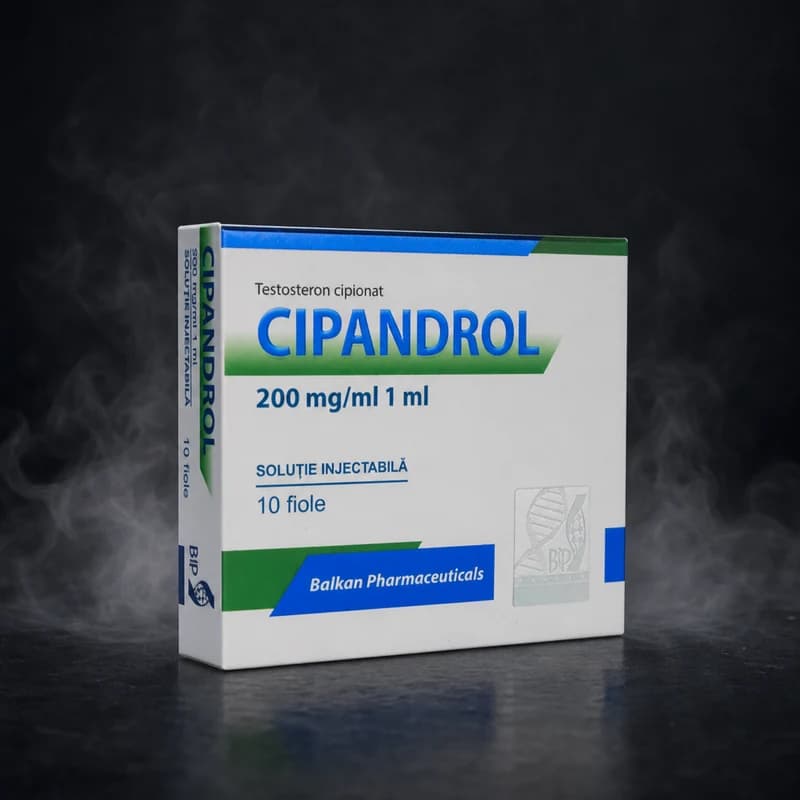 Established Brand