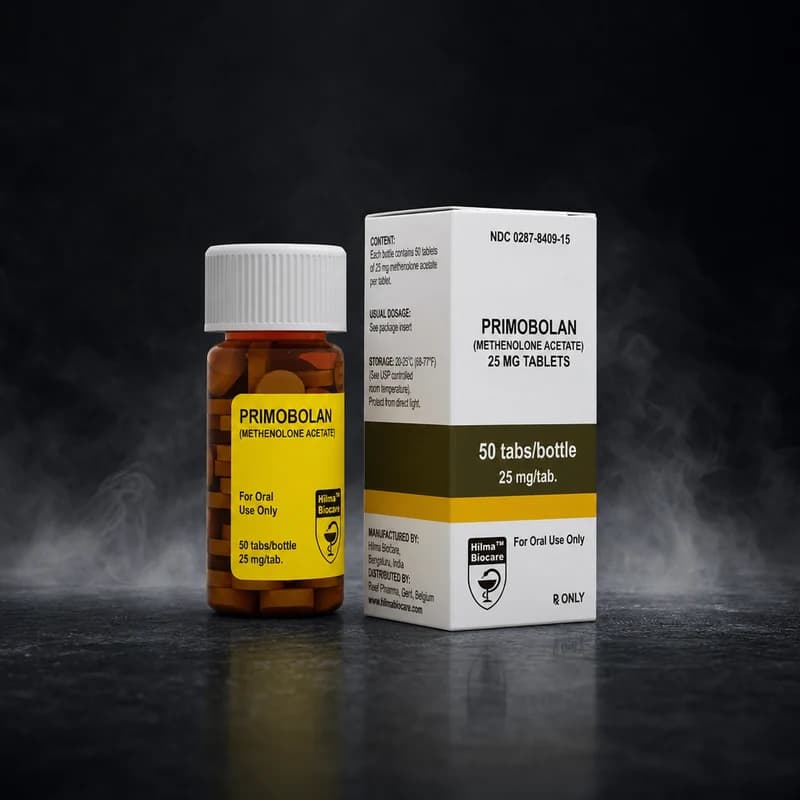
Contraindications: Not for use in individuals with diagnosed prostate carcinoma, hepatic adenoma, or a history of androgen-sensitive malignancy. Pregnancy and breastfeeding are absolute contraindications. Adolescents with open epiphyseal plates must not use this compound due to premature growth-plate closure risk.
Side Effects: Androgenic effects including accelerated scalp hair thinning in genetically predisposed individuals, sebaceous gland stimulation, and potential virilisation in females at doses above 20mg/day. Oral administration imposes hepatic processing load; while Methenolone Acetate is considered hepatically mild relative to 17-alpha-alkylated compounds, extended use warrants liver enzyme monitoring. HDL suppression has been documented in clinical literature under sustained oral androgen administration.
Monitoring: Schedule serum ALT/AST, total testosterone, LH, FSH, haematocrit, and lipid panel at baseline, mid-cycle (week 4–5), and within one week post-cycle. Blood pressure should be self-monitored weekly during the contest prep window. Athletes using Primobolan alongside other androgens should track all compounds collectively, not in isolation, when interpreting panel results.
PCT: Initiate post-cycle therapy within 3–5 days of the final tablet. A standard SERM-based protocol — Tamoxifen 20–40mg/day or Clomiphene 50mg/day — for four weeks is the minimum recommended recovery window. Where Primobolan has been stacked with suppressive androgens, PCT duration and SERM dosing should reflect the stack's overall suppression burden, not Methenolone alone.

 Lab Tested