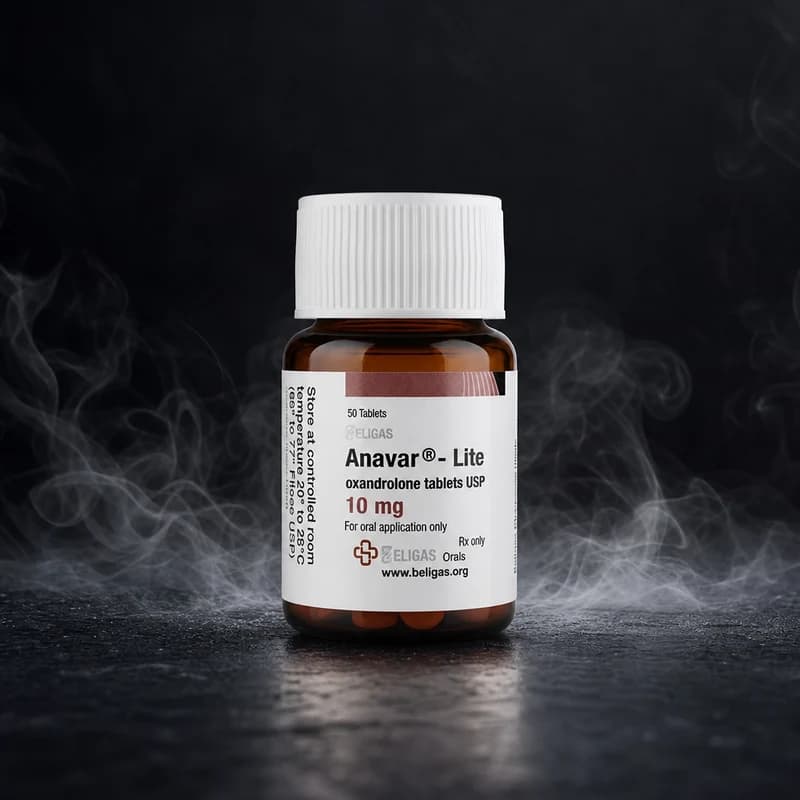
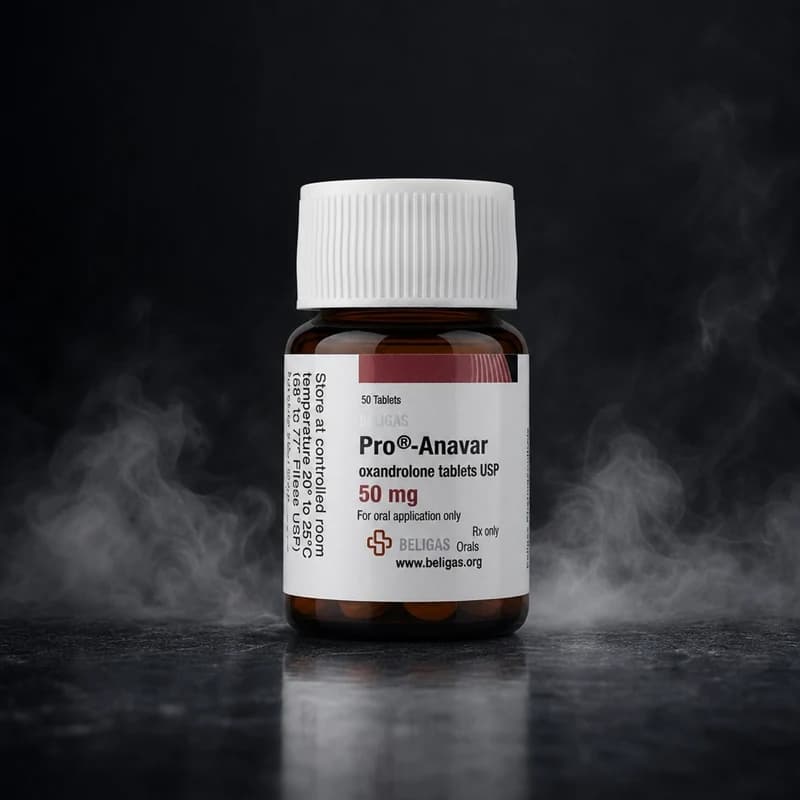
Contraindications: Oxandrolone is contraindicated in individuals with existing hepatic impairment, elevated baseline transaminases, active cardiovascular disease, or prostate pathology. Women who are pregnant or may become pregnant must not use this compound under any circumstances. Individuals currently using anticoagulants such as warfarin should note that Oxandrolone potentiates anticoagulant effect, requiring therapeutic dose adjustment under medical supervision.
Side Effects: PCT-phase Oxandrolone at 10–20mg per day carries a lower side-effect burden than cycle-phase dosing, but hepatic enzyme elevation (ALT/AST), HDL cholesterol suppression, and mild androgenic effects (acne, seborrhoea) remain possible. LDL/HDL lipid ratio disruption is the most clinically significant risk at any dose and should be monitored through bloodwork rather than managed reactively.
Monitoring: Baseline bloodwork before PCT commencement should cover complete blood count, lipid panel, liver function (ALT, AST, ALP), LH, FSH, and total testosterone. Repeat at week four of PCT and again two weeks after all compounds — including Oxandrolone — are discontinued. Liver enzyme values exceeding three times the upper limit of normal represent a clinical threshold requiring immediate compound cessation.
PCT: Oxandrolone during PCT does not replace SERM therapy — it functions as a lean-tissue bridge, not an HPG-axis stimulant. SERMs (tamoxifen or clomiphene) remain the primary driver of gonadotropin recovery and must be maintained for the full recommended duration regardless of Oxandrolone inclusion. Discontinue Oxandrolone at or before the point that bloodwork confirms testosterone has returned to pre-cycle baseline.

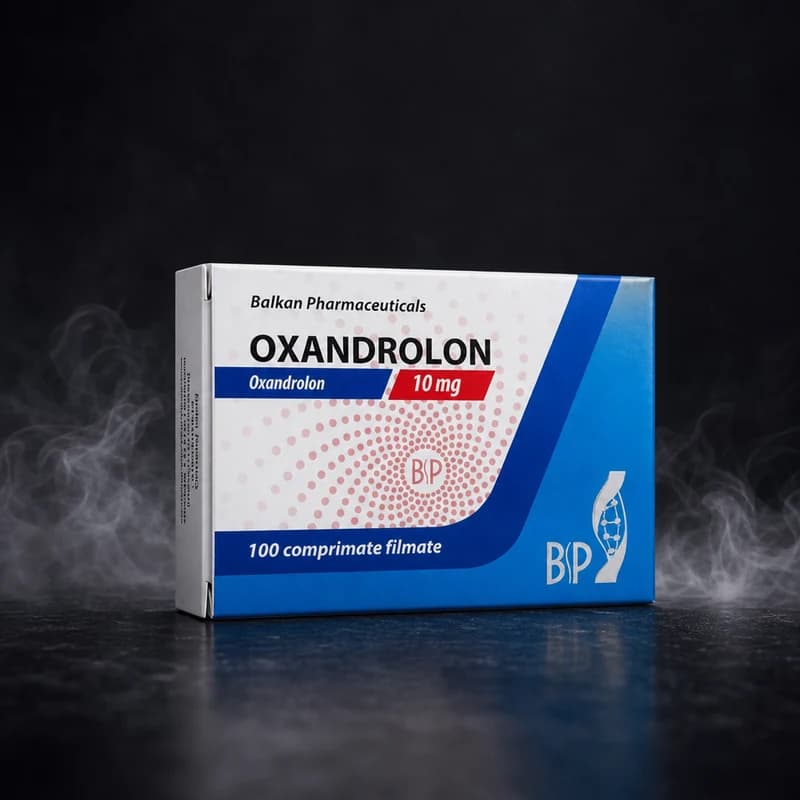 Lab Tested