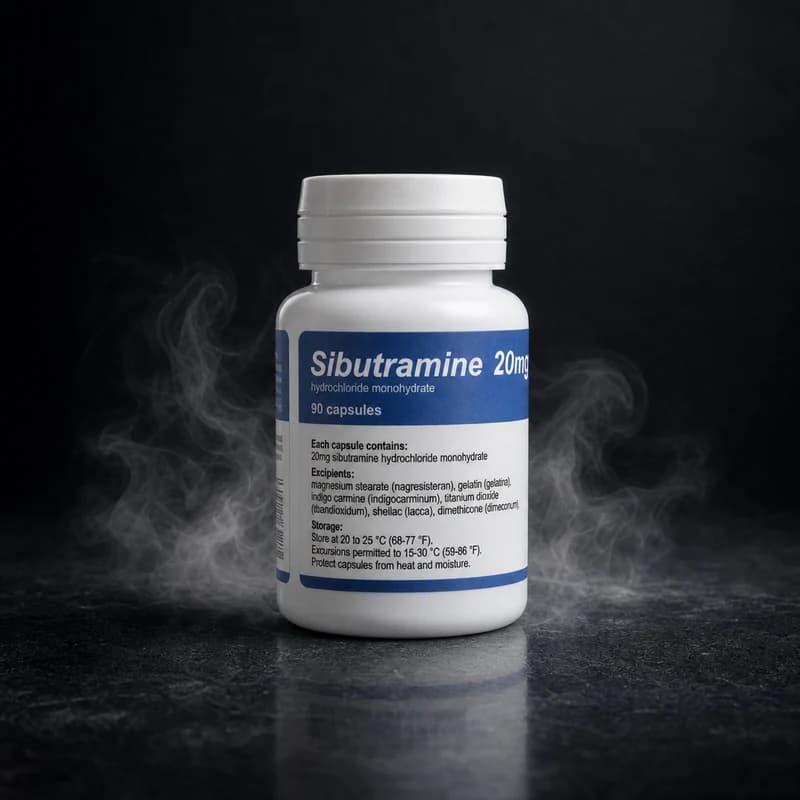
Contraindications: Sibutramine 20mg is contraindicated in individuals with a history of coronary artery disease, uncontrolled hypertension (systolic BP above 145 mmHg at rest), stroke, cardiac arrhythmia, or severe hepatic/renal impairment. Concurrent use with MAO inhibitors, SSRIs, SNRIs, triptans, or other serotonergic agents is strictly prohibited due to serotonin syndrome risk. Not for use in individuals under 18 or over 65 without specialist supervision.
Side Effects: Commonly reported effects at 20mg include dry mouth, constipation, insomnia (particularly with late-day dosing), headache, and elevated resting heart rate. Less commonly: palpitations, elevated blood pressure, anxiety, and paraesthesia. The 20mg dose carries a higher incidence of cardiovascular side effects than lower-strength formulations; individual sensitivity should be assessed during a mandatory titration phase.
Monitoring: Blood pressure and resting heart rate should be measured before initiating the protocol, at week two, and monthly thereafter. Any reading showing a resting heart rate persistently above 100 bpm or a systolic blood pressure increase of more than 10 mmHg above baseline warrants immediate protocol suspension. Liver enzyme panels (ALT, AST) are recommended at baseline and at 12 weeks. Keep a dosing log that records the exact time of each intake to identify timing-related cardiovascular patterns.
PCT: Sibutramine does not suppress the hypothalamic–pituitary–gonadal axis and does not require hormonal post-cycle therapy. A structured washout period of a minimum of four weeks following prolonged use (beyond 12 weeks) is advisable to allow adrenergic receptor sensitivity to normalise. If sibutramine has been used alongside anabolic androgenic steroids, AAS-related PCT should follow standard protocols independently of sibutramine discontinuation timing.

 Lab Tested