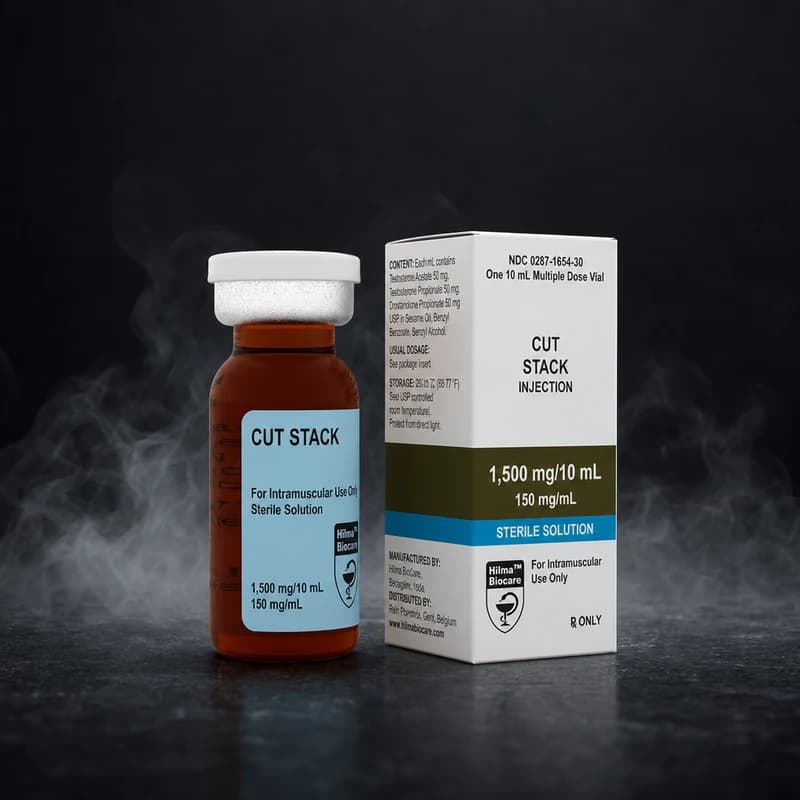
contraindications: Contraindicated in individuals with known hypersensitivity to any of the three active compounds or to oil-based injectable vehicles.
Not suitable for use in individuals with active prostate pathology, hepatic impairment, or cardiovascular risk factors including unmanaged dyslipidaemia.
Strictly contraindicated in women — virilising effects from Trenbolone Acetate and Drostanolone Propionate are irreversible.
Not for first-cycle or inexperienced users; receptor tolerance management requires working knowledge of androgenic pharmacology.
side_effects: Androgenic: acne, accelerated scalp hair loss in genetically predisposed individuals, prostate stimulation.
Cardiovascular: suppression of HDL cholesterol and elevation of LDL; Trenbolone Acetate is particularly associated with adverse lipid shifts — baseline and on-cycle lipid panels are required.
Neurological/Behavioural: trenbolone-associated aggression, insomnia, and night sweats are dose-dependent and more pronounced than with testosterone-only protocols.
Progestogenic suppression: Trenbolone Acetate's 19-nor structure produces significant HPA and HPGA axis suppression via progestogenic pathways — recovery without aggressive PCT is protracted.
monitoring: Perform baseline bloodwork prior to cycle start: full lipid panel, LFT, haematocrit, PSA (males 35+), and endogenous testosterone.
Mid-cycle monitoring (week 4–5) is advisable for lipid status and haematocrit given trenbolone's haematological effects.
Blood pressure should be self-monitored weekly — trenbolone-containing protocols are associated with elevated haematocrit and subsequent BP increases.
HPLC-verified batch documentation from BM Pharmaceuticals should be cross-referenced with purchase records to confirm product authenticity.
pct: Begin PCT 3–5 days after the final Mixobolin-200 injection — the 2–3 day half-lives of all three esters allow this earlier start compared to long-ester protocols.
A dual-SERM protocol combining Clomiphene Citrate and Tamoxifen Citrate is strongly recommended given the progestogenic suppression profile of Trenbolone Acetate; a single-agent SERM carries elevated risk of incomplete HPGA axis recovery.
Standard PCT duration: 4–6 weeks minimum; extend if LH/FSH and testosterone bloodwork at week 4 indicates insufficient recovery.
Do not attempt a mini-PCT or abbreviated SERM protocol after any cycle containing a 19-nor compound — progestogenic suppression requires a more sustained recovery intervention than ester half-life alone predicts.

 Recomp Optimizer