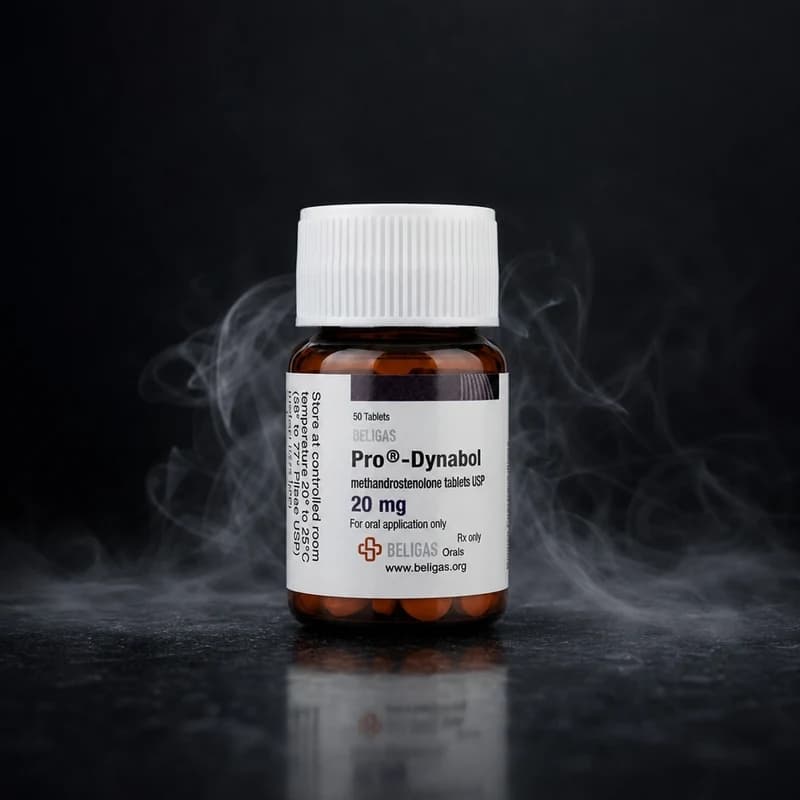
Contraindications: Methandienone is contraindicated in individuals with pre-existing hepatic dysfunction, prostatic hyperplasia, or a history of androgen-sensitive carcinoma. Women of childbearing potential should not use this compound due to virilisation risk. Individuals currently using anticoagulant therapy (e.g. warfarin) require specialist review, as 17α-alkylated androgens may potentiate anticoagulant activity.
Side Effects: Hepatotoxicity risk is elevated by 17α-alkylation and scales with both dose and cycle duration; serum transaminase elevation (ALT, AST) is the primary monitored marker. Estrogenic side effects — including fluid retention and gynecomastia — result from aromatisation; an aromatase inhibitor should be available. Androgenic effects (acne, scalp hair thinning) depend on individual genetic sensitivity. Cardiovascular risk includes suppression of HDL cholesterol and elevated LDL, detectable within the first two weeks of use via standard lipid panels.
Monitoring: Obtain baseline liver-function tests (ALT, AST, GGT) and a full lipid profile before the first tablet. Re-test liver enzymes at week four and at cycle end. Blood pressure should be measured weekly, as sodium-retaining effects can contribute to acute hypertensive episodes. Haematocrit and haemoglobin should be checked in cycles exceeding six weeks.
PCT: Endogenous testosterone suppression begins within the first week of Methandienone use. Post-cycle therapy using a SERM — typically Nolvadex (Tamoxifen) at 20–40 mg/day or Clomid at 50 mg/day — should commence no earlier than 24 hours after the final tablet, given Methandienone's short clearance window. Standard PCT duration is four weeks. TUDCA or UDCA at 500 mg/day throughout the cycle supports hepatocyte function during 17α-alkylated compound exposure.

 Lab Tested