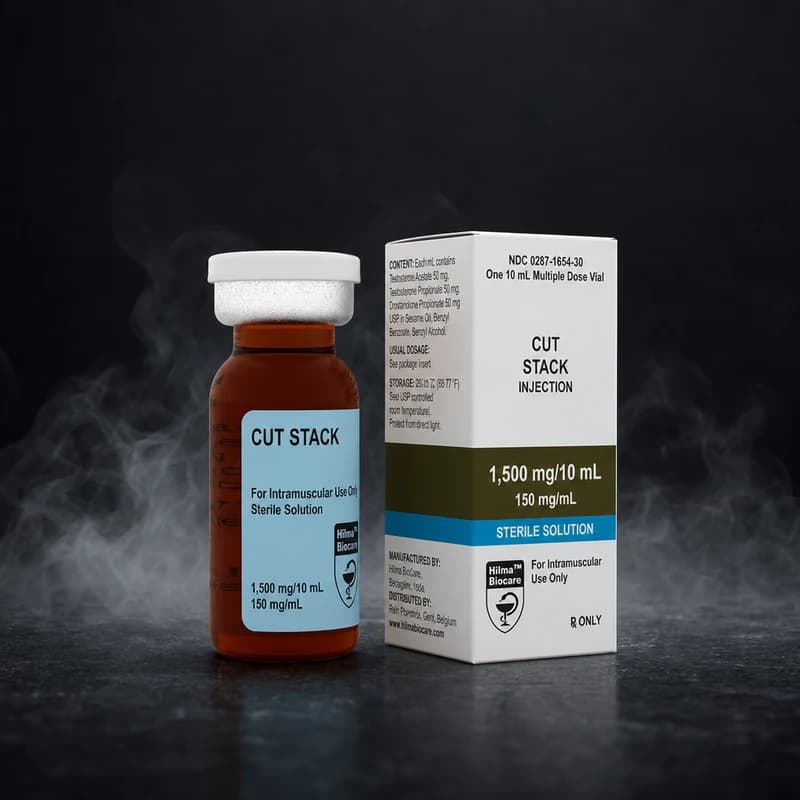
contraindications: Contraindicated in individuals with prostate cancer, breast cancer, or hypercalcaemia regardless of compound selection.
Not suitable for female athletes due to the androgenic potency of all three active compounds, particularly Trenbolone Acetate.
Cardiovascular disease, uncontrolled hypertension, or left ventricular hypertrophy are absolute contraindications.
Do not use if allergic to any component of the formulation including carrier oil or solvent excipients.
side_effects: Trenbolone Acetate is associated with transient cough reflex ('tren cough') immediately post-injection in a subset of users; slow injection technique reduces incidence.
Androgenic effects include acne, accelerated scalp hair thinning in genetically predisposed individuals, and increased sebum production.
Cardiovascular effects: haematocrit elevation, LDL increase, HDL suppression — require lipid monitoring throughout the cycle.
Neurological: vivid dreams and sleep disruption are common with Trenbolone Acetate; night sweats may occur.
Repeated injection at the same site without adequate rotation may lead to subcutaneous nodule formation or localised fibrosis over time.
monitoring: Full blood count and lipid panel before cycle commencement and at mid-cycle (week 4–5) minimum.
Blood pressure monitoring twice weekly throughout the cycle — high-concentration trenbolone accelerates haematocrit rise.
Liver enzyme panel (ALT/AST) at cycle start and end; injectable blends carry lower hepatic burden than oral compounds but monitoring remains standard practice.
Prolactin and oestradiol levels should be checked mid-cycle given Trenbolone's progestogenic activity and Testosterone Propionate's aromatisation potential.
pct: PCT begins approximately 3–5 days after the final injection of Cut Mix 300, utilising propionate and acetate ester clearance timelines.
A SERM-based protocol (Nolvadex 40/40/20/20mg or Clomid 50/50/25/25mg over 4 weeks) is the standard approach; individual suppression depth determines whether 4 or 6 weeks is appropriate.
Bloodwork at the end of PCT week 4 confirms whether hormonal recovery is on track or whether the protocol requires extension.
A dopamine agonist (Cabergoline) may be warranted if prolactin elevation is confirmed via blood panel during or after the cycle.

 Hardcore Cutting