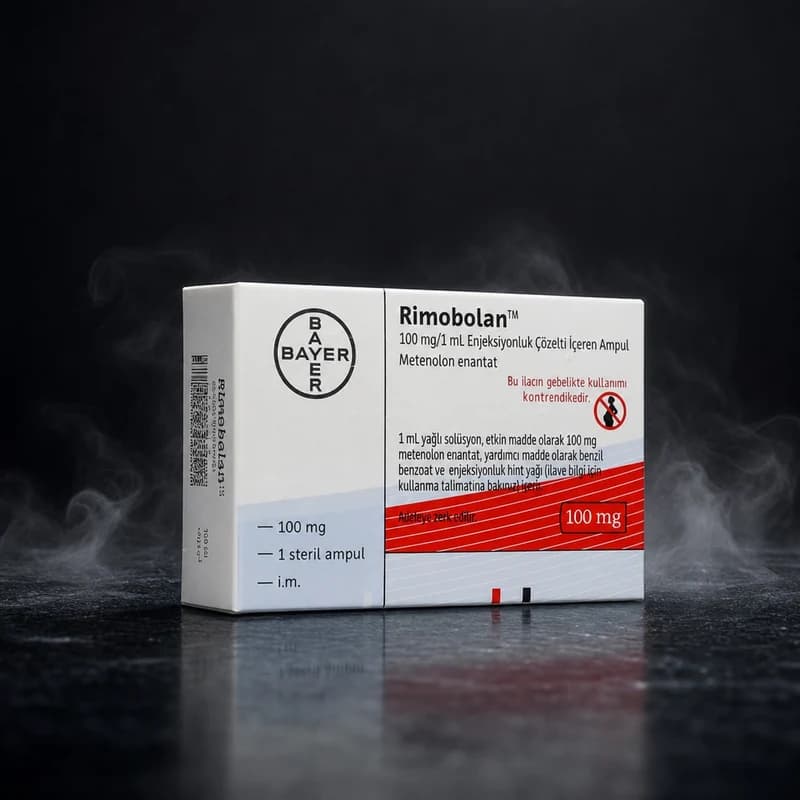
contraindications: Methenolone Enanthate is contraindicated in individuals with androgen-sensitive malignancies (prostate or breast carcinoma), established hepatic dysfunction, or hypersensitivity to any ampoule excipient including sesame or other carrier oils. Women of reproductive age should not use this compound given the virilisation risk associated with prolonged androgenic exposure.
side_effects: Androgenic suppression of the HPG axis (reduced LH, FSH, and endogenous testosterone) is the most clinically consistent effect. Mild androgenic effects including accelerated scalp hair miniaturisation in genetically predisposed individuals may occur. Co-administration with GH secretagogue peptides can independently elevate fasting glucose via GH-mediated insulin antagonism; this is a peptide-class effect rather than a Methenolone-specific one.
monitoring: Run a full panel (IGF-1, HOMA-IR, LH, FSH, haematocrit, lipid fractions, and hepatic transaminases ASAT and ALAT) at baseline, week four, and week eight. In peptide-inclusive stacks, IGF-1 and HOMA-IR require separate tracking from androgenic suppression markers because their source variables — GH-axis activity versus HPG axis suppression — are mechanistically independent.
pct: Allow sufficient plasma clearance time after the final Methenolone Enanthate injection before commencing SERM-based post-cycle therapy. Timing should be guided by week-fourteen LH and FSH bloodwork confirming actual suppression depth. Clomiphene or tamoxifen at standard recovery doses are the established SERM options; peptides with no hormonal axis activity (BPC-157, TB-500) may be continued through the PCT window without conflict.

 Established Brand