Established Brand
Primobol 100mg/ml 10x1ml Ampullen by Balkan Pharmaceuticals
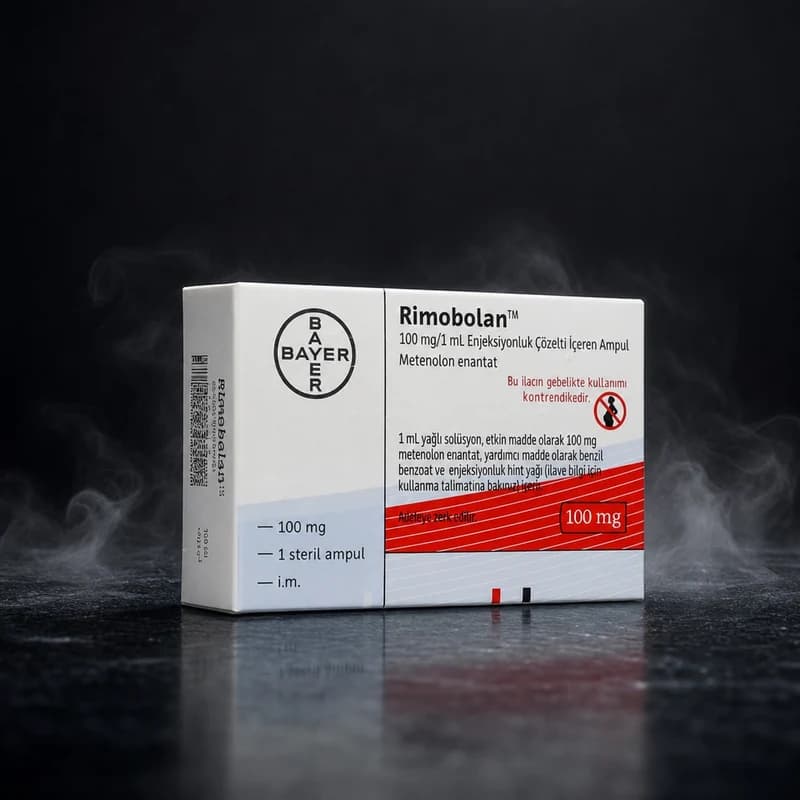
Primobol by Balkan Pharmaceuticals delivers Methenolone Enanthate at 100 mg/ml across ten glass-fusion sealed, single-dose ampoules — a format rooted in the original Schering AG clinical presentation that has defined this compound since its 1960s introduction for muscle-wasting indications. The 100 mg/ml concentration reflects the benchmark established during Methenolone's first decade of human clinical use, situating Primobol as a direct continuation of a molecule with more than sixty years of documented pharmacological history. Each ampoule is manufactured under GMP Annex 1 aseptic conditions at Balkan Pharmaceuticals' Chișinău facility; HPLC potency analysis and LAL endotoxin screening are completed at batch level before release.
€55.00