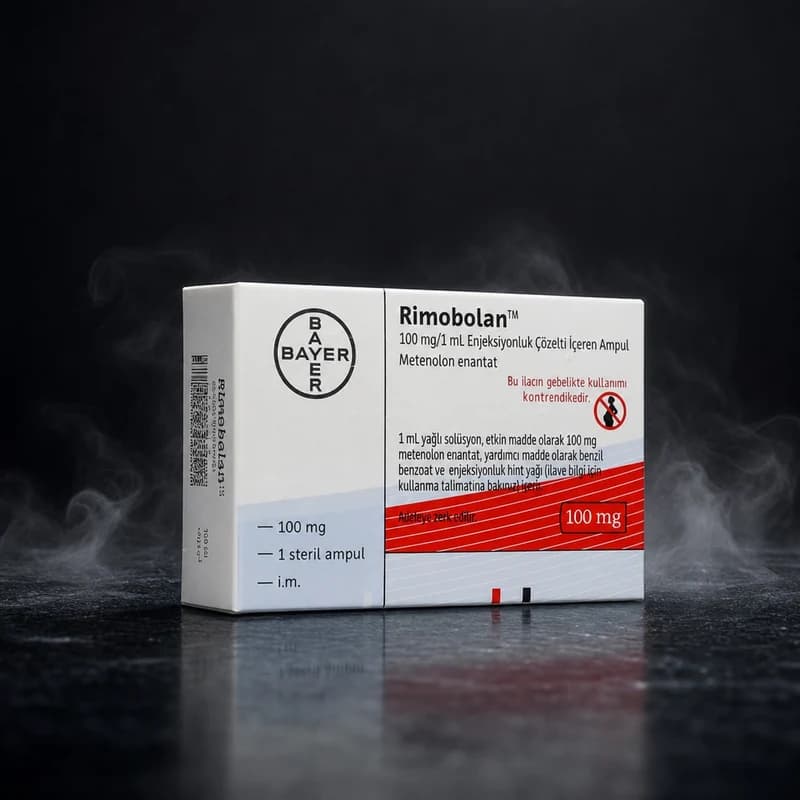
Contraindications: Methenolone Enanthate is contraindicated in individuals with known androgen-sensitivity disorders, active or suspected hormone-responsive malignancies (particularly prostate adenocarcinoma), severe hepatic impairment, or uncontrolled hyperlipidaemia. Females who are pregnant or breastfeeding must not use this compound. Individuals under 21 years of age should not use injectable anabolic steroids.
Side Effects: Potential androgenic effects include accelerated male-pattern hair thinning in genetically predisposed individuals, acne at sebaceous-dense skin sites, and mild virilisation in female users even at conservative doses. Suppression of endogenous testosterone production occurs with all exogenous anabolic androgens; the degree correlates with dose and cycle duration. Lipid-profile changes — specifically HDL reduction and LDL elevation — have been documented with Methenolone use and should be monitored via blood lipid panels.
Monitoring: Baseline bloodwork before cycle initiation should include: full lipid panel (HDL, LDL, triglycerides), haematocrit and haemoglobin, LH/FSH and total testosterone, and hepatic enzyme markers (ALT, AST). Repeat haematological and lipid assessment at weeks 4–6 of an active cycle. Intramuscular injection sites should be inspected for signs of abscess or nodule formation; persistent nodular inflammation warrants medical evaluation.
PCT: Because Methenolone Enanthate suppresses the hypothalamic-pituitary-gonadal axis through negative feedback on LH and FSH secretion, post-cycle therapy using a SERM such as Tamoxifen or Clomiphene is recommended following cycle completion. The timing of SERM initiation after the final injection must account for the enanthate ester's multi-day depot clearance window; initiating PCT prematurely while depot levels remain active reduces its effectiveness.

 Established Brand