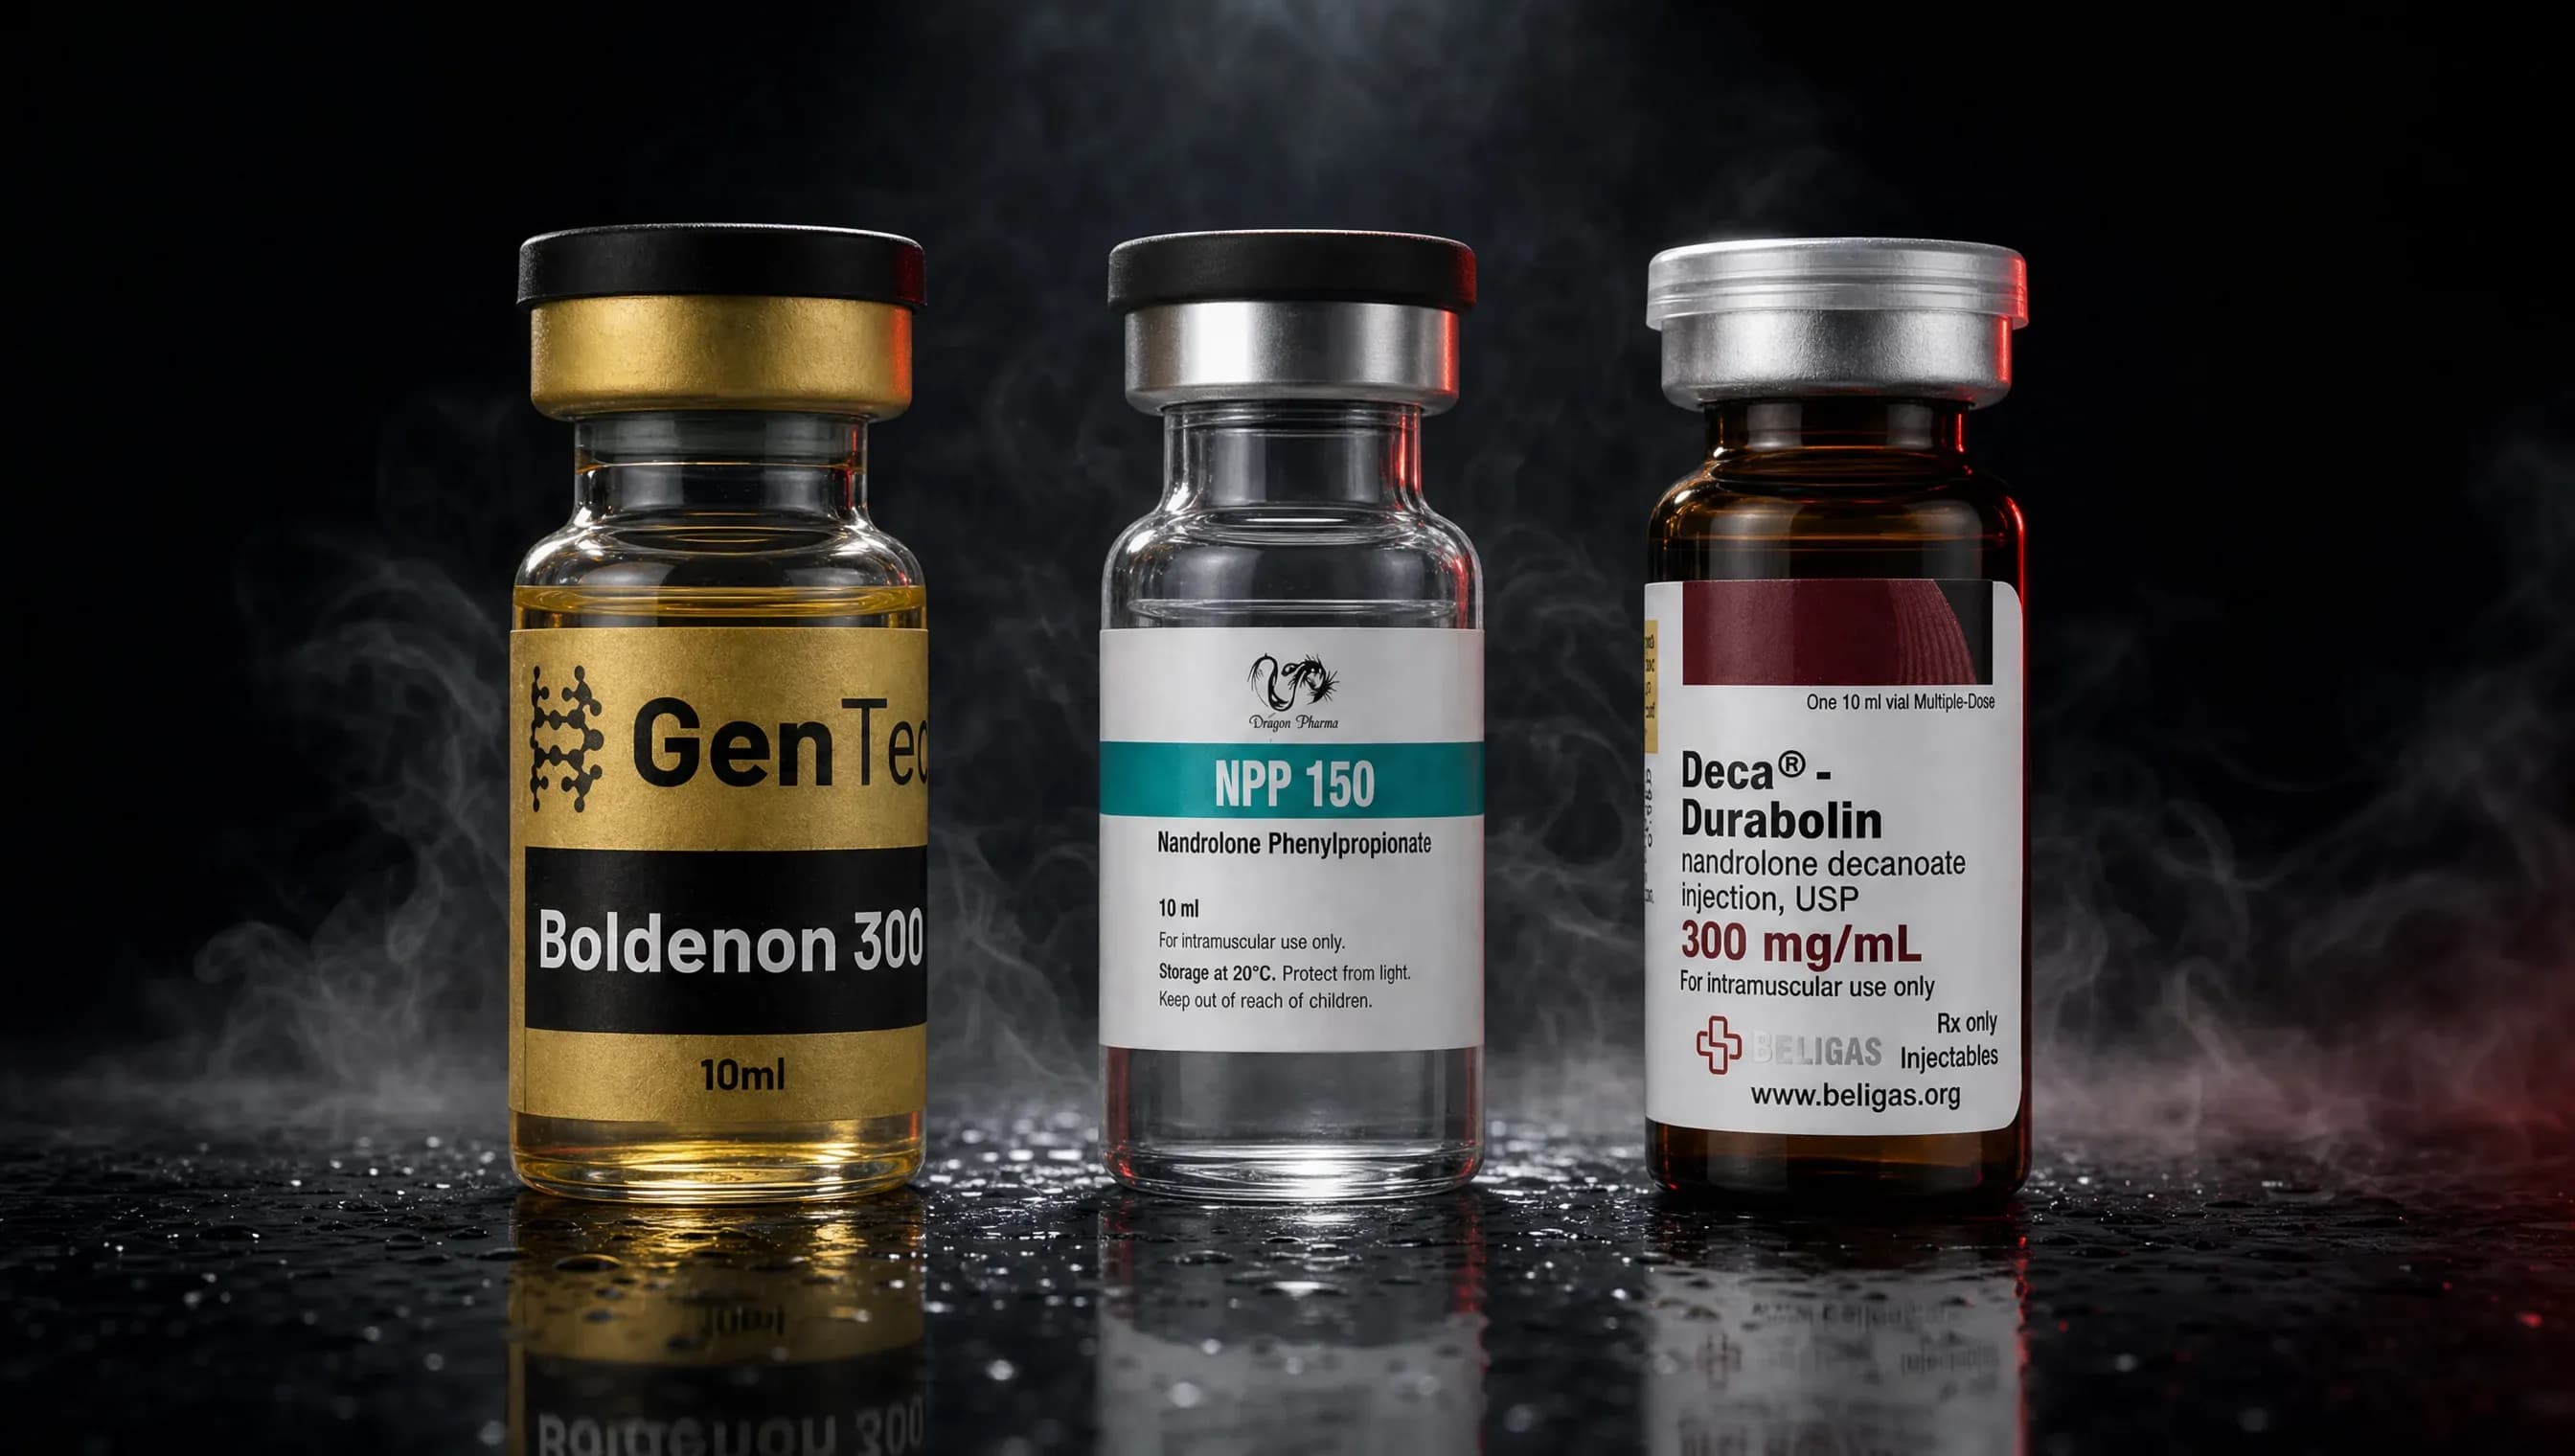
Equipoise vs Deca vs NPP: Boldenone and Nandrolone Esters Compared
Equipoise drives lean, dry gains but demands strict haematocrit monitoring every 6 weeks.
Equipoise vs Deca vs NPP: Boldenone and Nandrolone Esters Compared
TL;DR- Equipoise drives lean, dry gains but demands strict haematocrit monitoring every 6 weeks.- Deca-Durabolin offers superior joint lubrication and mass but carries high "Deca Dick" risk.- NPP delivers identical nandrolone pharmacology with far faster ester clearance and PCT timing.- Boldenone aromatises at roughly 50% the rate of testosterone; nandrolone barely aromatises at all.- All three compounds require a testosterone base to preserve libido and dopaminergic function.- NPP is the lower-risk entry point for first-time nandrolone users due to its short half-life.
Boldenone undecylenate (sold as Equipoise) is a synthetic testosterone derivative characterised by a C1–C2 double bond that dramatically reduces its affinity for aromatase, yielding an oestrogen conversion rate roughly half that of testosterone itself. Nandrolone — the active molecule shared by both Deca-Durabolin and NPP — is a 19-nor steroid, meaning it lacks the C19 methyl group present in testosterone, which grants it meaningful progestational activity and a potent suppressive effect on the hypothalamic–pituitary–gonadal (HPG) axis. These three injectable anabolics are frequently grouped together because all three suit a quality-muscle-building goal, yet their side-effect profiles, ester kinetics, and monitoring requirements diverge sharply. This article breaks down the mechanisms, practical protocols, and risk profiles of each compound as of August 2026.
Pharmacology and Molecular Differences
The C1–C2 double bond in boldenone is not cosmetic chemistry — it repositions electrons across the A-ring, reducing the molecule's binding efficiency at the aromatase enzyme (CYP19A1) and eliminating the 5α-reductase conversion pathway that produces dihydrotestosterone. Instead, boldenone undergoes 5α-reduction to dihydroboldenone, which retains reasonable androgenic potency without the scalp-aggressive profile of DHT.
Nandrolone's 19-nor structure tells a different story. Without C19, nandrolone is a poor aromatase substrate — estimated aromatisation is under 20% relative to testosterone — but it binds the progesterone receptor with measurable affinity, activating downstream prolactin secretion in susceptible individuals. The same structural change means 5α-reductase converts nandrolone to dihydronandrolone (DHN), a molecule with very weak androgenic activity at androgen receptors in penile and neurological tissue. This is the biochemical root of the libido problems associated with nandrolone use.
Ester Kinetics: Half-Lives and Injection Frequency
The ester attached to each compound governs how quickly plasma concentrations rise, stabilise, and fall — and that directly dictates cycle length, injection schedule, and the wait before post-cycle therapy (PCT) begins.
Parameter | Equipoise (EQ) | Deca-Durabolin | NPP |
|---|---|---|---|
Active molecule | Boldenone | Nandrolone | Nandrolone |
Ester | Undecylenate | Decanoate | Phenylpropionate |
Plasma half-life | ~14 days | ~6–7 days | ~2–3 days |
Injection frequency | Once weekly | Once weekly | Every other day |
Steady-state reached | Week 6–8 | Week 4–5 | Week 2–3 |
Time to PCT after last pin | 21–28 days | 18–21 days | 3–7 days |
Typical weekly dose | 300–600 mg | 200–400 mg | 150–300 mg |
Minimum cycle length | 14–16 weeks | 12–14 weeks | 8–10 weeks |
Equipoise's undecylenate ester is the longest of the three, which is why cycles shorter than 14 weeks genuinely waste the compound — users who only run it for 10 weeks spend the majority of that time below meaningful steady-state concentrations. NPP's phenylpropionate ester, by contrast, reaches a working plasma level within two weeks of every-other-day dosing, making it ideal for shorter blocks or situations where fast course-correction is needed.
Equipoise and Haematocrit: The Risk You Cannot Ignore
Boldenone stimulates erythropoiesis more aggressively than virtually any other non-EPO compound used in recreational bodybuilding. The mechanism involves upregulation of endogenous erythropoietin production, amplified by the compound's long tissue exposure courtesy of the 14-day ester. Haematocrit values above 54% are commonly reported in EQ cycles exceeding 12 weeks at doses of 400 mg per week or higher — a threshold associated with significantly increased blood viscosity and cardiovascular strain.
Practical monitoring protocol for any EQ cycle:
- Baseline bloods before cycle start: haematocrit, haemoglobin, blood pressure, lipid panel.
- Week 6 retest: haematocrit and blood pressure minimum.
- At haematocrit >52%: reduce EQ dose by 100–150 mg weekly and increase daily water intake to a minimum of 3 litres.
- At haematocrit >54%: consider therapeutic phlebotomy (450–500 ml), halt dose escalation, and reassess at week 10.
Nandrolone compounds also elevate haematocrit, but less dramatically. Combined EQ + nandrolone cycles compound this risk without proportionate benefit — stacking both is rarely justified.
Nandrolone, Libido, and the "Deca Dick" Mechanism
"Deca Dick" — the colloquial term for nandrolone-induced erectile dysfunction and libido suppression — results from three overlapping mechanisms operating simultaneously. First, DHN (the 5α-reduced metabolite of nandrolone) is a weak androgen at penile smooth muscle and neurological androgen receptors, providing insufficient stimulation compared to DHT. Second, nandrolone's progesterone receptor activity can suppress gonadotropin-releasing hormone (GnRH) pulsatility further, deepening HPG axis suppression beyond what testosterone alone would cause. Third, prolactin elevation — mediated partly through dopamine D2 receptor competition — reduces sexual motivation at the hypothalamic level.
NPP presents the same three mechanisms, but with one critical practical advantage: if symptoms emerge, the phenylpropionate ester clears within 3–5 days after the last injection. Decanoate users may wait two to three weeks for the compound to fall to negligible plasma levels, extending the symptomatic period considerably.
Community-validated mitigation strategies:
- Maintain a testosterone:nandrolone ratio of at least 1:1 by weekly milligram dose; many experienced users prefer 1.5:1.
- Monitor serum prolactin at baseline and at week 6–8.
- If prolactin is elevated and symptomatic, cabergoline (a dopamine D2/D4 agonist targeting pituitary lactotrophs) at 0.25–0.5 mg twice weekly is the standard pharmacological intervention — not prophylactic use.
- Pyridoxal-5-phosphate (P5P, the active form of vitamin B6) at 100–200 mg daily has modest prolactin-modulating evidence and a negligible side-effect profile.
Joint Health: Where Nandrolone Has a Genuine Edge
Both nandrolone esters provide measurable joint comfort improvements — a benefit attributed to increased synovial fluid viscosity, upregulated collagen synthesis in connective tissue, and possible direct anti-inflammatory effects at glucocorticoid receptors (nandrolone shows weak glucocorticoid receptor binding). Athletes with chronic joint pain, rotator cuff irritation, or hip discomfort during heavy loading phases often report significant subjective improvement within four to six weeks of nandrolone use at 200–300 mg weekly.
Boldenone does not replicate this effect. Its drier, less water-retentive profile means joints receive no meaningful lubrication benefit — and in some users who experience E2 suppression from EQ's competition with testosterone at the aromatase enzyme, joint discomfort can actually worsen due to insufficient oestradiol. If joint support is a primary goal, nandrolone at modest doses outperforms boldenone substantially.
Choosing Your Compound: Practical Decision Framework
Equipoise suits you if: you want gradual, dry muscle accrual over a 16-week lean-bulk phase, you have no existing haematocrit concerns, and you are willing to run bloods at weeks 6 and 12. It pairs cleanly with a testosterone base and an oral such as anavar or turinabol for the final four weeks.
Deca-Durabolin suits you if: you are in a mass phase, you have chronic joint discomfort, and you are comfortable with a 12–14 week minimum commitment plus the 18–21 day PCT delay. At 300 mg weekly with 500 mg testosterone, it reliably produces meaningful size without requiring aggressive dosing.
NPP suits you if: you are running nandrolone for the first time and want the ability to discontinue quickly, if your cycle window is 8–10 weeks, or if previous Deca cycles produced libido issues you want faster control over. Every-other-day pinning is more demanding, but the pharmacokinetic flexibility is worth it for most beginners to nandrolone.
FAQ
Does Equipoise lower oestradiol levels?
Boldenone competes with testosterone for aromatase (CYP19A1) binding sites, which can reduce the conversion of testosterone to oestradiol in users running both compounds simultaneously. Some individuals experience measurably low E2 — presenting as joint aches, low libido, and mood disruption — without any aromatase inhibitor on board. Manage by symptom and bloodwork, not by reflexively adding an AI.
Is cabergoline necessary on every nandrolone cycle?
No. Cabergoline is a potent dopamine D2/D4 agonist with its own risk profile, including nausea, orthostatic hypotension, and cardiac valve concerns at sustained high doses. It should be reserved for confirmed, symptomatic prolactin elevation verified by serum testing — not used prophylactically on every nandrolone cycle regardless of bloodwork.
Why must EQ cycles be at least 14 weeks long?
The undecylenate ester produces a plasma half-life of approximately 14 days, meaning steady-state concentrations are not reached until weeks six to eight. Cycles under 12 weeks spend the majority of their duration at sub-optimal blood levels, making shorter EQ cycles an inefficient use of both the compound and the associated health risks.
Can NPP and Equipoise be stacked together?
It is chemically possible but rarely advisable. Both compounds independently raise haematocrit and erythropoietin activity — combining them compounds cardiovascular risk without delivering proportionate muscle-building benefit over a single well-dosed compound plus testosterone. One compound per cycle alongside a testosterone base is the standard lower-risk framework.
When should PCT start after each compound?
After NPP, begin PCT 3–7 days post-last injection. After Deca-Durabolin, wait 18–21 days. After Equipoise, wait 21–28 days. Nandrolone's deep HPG axis suppression often warrants HCG use in the final two weeks of cycle before SERM introduction to restore testicular sensitivity.
Conclusion
Equipoise, Deca-Durabolin, and NPP each solve the same problem — building quality muscle — with meaningfully different trade-offs. Boldenone demands haematocrit discipline in exchange for dry, gradual gains and a relatively clean hormonal profile. Nandrolone — whether delivered slowly via decanoate or rapidly via phenylpropionate — provides superior joint support and dense mass, offset by genuine libido and prolactin risks that require active management. NPP narrows that risk window through faster ester clearance, making it the rational starting point for any athlete exploring nandrolone for the first time. Whichever compound you choose, a testosterone base, pre-cycle bloodwork, and mid-cycle monitoring at week six are non-negotiable foundations of a responsible protocol.


